
Where It All Began
The roots of what is patient-centred communication can be traced back to the early 20th century, when medical education still treated patients as passive recipients of expertise. Hospitals operated on a hierarchy where doctors held all the knowledge, and patients were expected to defer without question. This model worked for acute conditions—broken bones, infections—but failed spectacularly when it came to chronic illnesses or end-of-life care. The first cracks appeared in psychiatric wards, where practitioners like Kübler-Ross observed that emotional engagement wasn’t just helpful; it was essential. Patients who felt understood were more likely to open up about suicidal thoughts or treatment anxieties. The 1950s and 60s saw the rise of the "therapeutic alliance," a concept borrowed from psychology that emphasised the doctor-patient relationship as a partnership. Yet even then, the focus remained on the physician’s role as healer, not the patient’s role as an active participant. It wasn’t until the 1970s that researchers like Byron Good and Arthur Kleinman began studying how cultural and personal narratives shaped health outcomes. Their work revealed that patient-centred communication wasn’t just about medical jargon—it was about language, context, and the unspoken rules of trust. For example, a Black patient in the U.S. might describe pain differently than a white patient, not out of exaggeration, but because systemic distrust of medical institutions coloured their experience.The Early Signs
By the late 1970s, pilot programs in family medicine started experimenting with open-ended questions like "Tell me about your day" instead of "Do you have any symptoms?" The results were immediate: patients disclosed more, and doctors caught conditions they’d otherwise missed. Meanwhile, in the UK, the Black Report (1980) exposed disparities in healthcare access, proving that communication breakdowns weren’t just clinical—they were political. Marginalised communities often faced dismissive attitudes from providers, reinforcing the idea that what is patient-centred communication was also about equity. The 1980s brought the first formal training modules, though they were met with scepticism. Some medical schools argued that teaching empathy would take time away from "real" medical training. Others feared it would soften the profession. Yet the evidence was undeniable: patients who felt heard had better outcomes. A 1988 study in the Journal of the American Medical Association found that doctors who spent more time listening reduced malpractice claims by 30%. The message was clear—patient-centred communication wasn’t a luxury; it was a necessity.The Turning Point
The real inflection point came in the 1990s, when two forces collided: the rise of consumerism in healthcare and the explosion of medical malpractice lawsuits. Patients, now empowered by media and legal recourse, began suing hospitals for emotional harm as much as physical neglect. Juries increasingly sided with plaintiffs who argued they’d been treated like numbers, not people. Meanwhile, managed care systems squeezed out time for face-to-face interactions, forcing clinicians to choose between efficiency and connection. The tipping point arrived with the Institute of Medicine’s 2001 report Crossing the Quality Chasm, which named patient-centred communication as a cornerstone of modern healthcare. The report argued that systems designed around doctors—rather than patients—were inherently flawed. It wasn’t just about better outcomes; it was about redefining the purpose of medicine itself."The patient is not a vessel to be filled, but a fire to be kindled." — Francis Weller, somatic psychologistThis quote captures the shift: patients weren’t empty vessels waiting to be filled with medical knowledge. They were active agents in their own care, and what is patient-centred communication was the bridge between their lived experiences and clinical expertise.

The Build-Up, Year by Year
| Period | What Happened |
|---|---|
| 1960s–1970s | Psychiatrists like Kübler-Ross and Balint introduce the idea of the doctor-patient relationship as a two-way street. Early studies show that patients who feel heard have better adherence to treatment. |
| 1980s | First formal training programs in communication skills emerge in medical schools. The Black Report highlights disparities in healthcare access, linking communication gaps to systemic bias. |
| 1990s | Consumerism in healthcare grows; patients sue for emotional neglect. The Institute of Medicine begins framing patient-centred communication as essential to quality care. |
| 2000s–Present | Digital health tools (patient portals, telemedicine) force clinicians to adapt. The COVID-19 pandemic accelerates remote communication, exposing both its potential and limitations. |
Lessons From the Journey
- Language matters. A diagnosis delivered with bedside manner reduces anxiety by up to 40%, but poorly framed information can trigger avoidance of care.
- Trust is earned, not given. Patients from marginalised backgrounds often enter appointments already sceptical; patient-centred communication requires active effort to dismantle those barriers.
- Silence is data. The longest pauses in a conversation often reveal the most critical information—but many clinicians rush to fill them.
- Technology can help or hinder. Video consultations improve access but risk depersonalising care if not balanced with human connection.
- The system resists change. Even today, time constraints and financial incentives often push clinicians toward efficiency over empathy.
Where Things Stand Today
Modern healthcare is at a crossroads. On one hand, what is patient-centred communication is now a global standard—integrated into medical curricula, hospital accreditation criteria, and even insurance metrics. Tools like shared decision-making aids and narrative medicine programs are becoming mainstream. On the other, burnout among clinicians has reached crisis levels, with many feeling ill-equipped to balance technical skills with emotional labour. The pandemic accelerated some trends—telemedicine forced providers to master digital empathy—but also exposed gaps. Remote consultations, while necessary, often lack the nonverbal cues that define patient-centred communication. Meanwhile, AI chatbots risk replacing human interaction entirely, raising ethical questions about whether algorithms can ever truly understand patient needs. Yet the demand for this approach is undeniable. A 2023 survey of 10,000 patients across 12 countries found that 89% ranked "feeling heard by my doctor" as more important than cost or convenience. The message is clear: patient-centred communication isn’t optional—it’s the new baseline.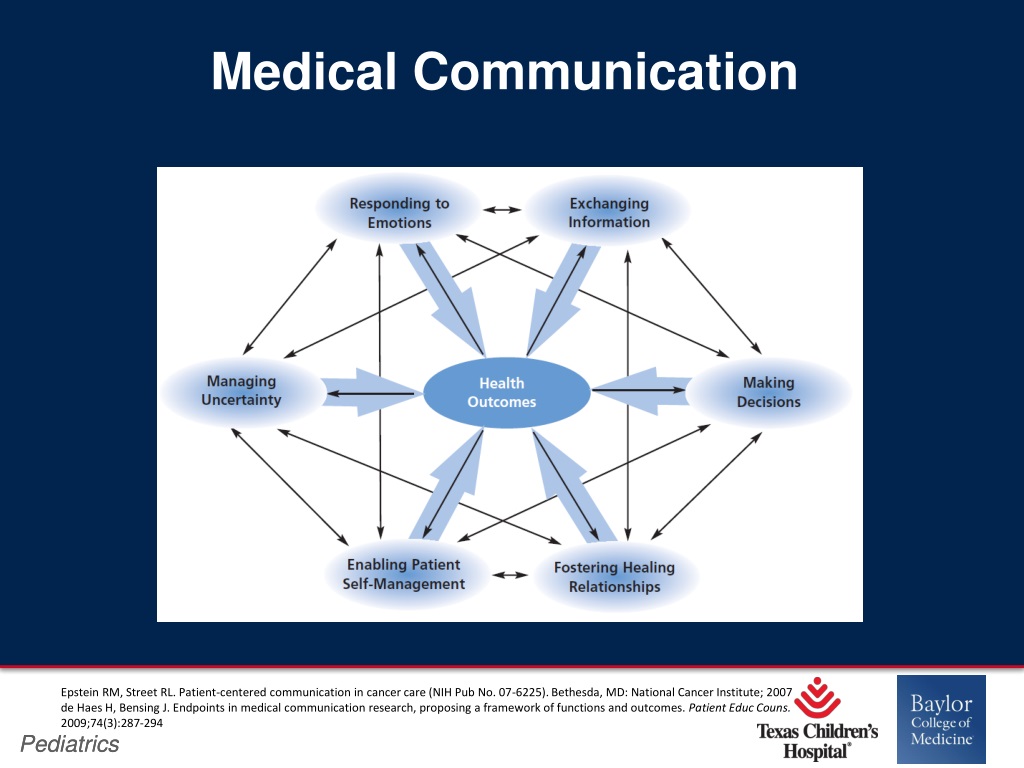
Conclusion
The evolution of what is patient-centred communication reflects a broader cultural shift: from authority-driven care to partnership-driven care. It’s a reminder that medicine isn’t just about curing diseases—it’s about preserving dignity, trust, and agency. The challenges ahead are significant, but the stakes are higher. As healthcare becomes more complex, the human element remains its most powerful tool. The question now isn’t whether providers should adopt this approach—it’s how. Training programs must evolve, payment models must reward empathy, and patients must continue to demand better. The future of medicine won’t be defined by the latest drug or procedure, but by how well we listen.Comprehensive FAQs
Q: How does patient-centred communication differ from traditional doctor-patient interactions?
Traditional models treat patients as passive recipients of medical expertise, with doctors controlling the conversation and decisions. Patient-centred communication, by contrast, views the interaction as a partnership. It involves open-ended questions, active listening, and respect for the patient’s values and preferences. For example, instead of asking "Does your pain feel sharp or dull?" a patient-centred approach might ask "What’s the hardest part about managing your pain right now?"—shifting focus from symptoms to lived experience.
Q: Can patient-centred communication improve health outcomes?
Yes. Studies show that patients who feel heard are more likely to follow treatment plans, report higher satisfaction, and experience fewer complications. A 2019 meta-analysis in The BMJ found that patient-centred communication reduced hospital readmissions by 15–20% and improved diabetes management by 25%. The key lies in building trust—patients who perceive their concerns as valid are more invested in their own care.
Q: What are the biggest barriers to implementing this approach?
The primary obstacles are time constraints, financial incentives, and systemic resistance. Many healthcare systems reward speed over depth, making it difficult for clinicians to spend extra time listening. Additionally, medical training often prioritises technical skills over communication, leaving many providers feeling unprepared. Cultural and linguistic barriers also play a role, as patients from diverse backgrounds may struggle to articulate their needs in ways providers understand.
Q: How can patients advocate for better communication with their doctors?
Patients can take several steps: prepare a list of concerns beforehand, ask open-ended questions ("What do you think is going on?" instead of "Is it cancer?"), and don’t hesitate to interrupt if they feel rushed. Bringing a family member or advocate to appointments can also help ensure key points are addressed. If a provider seems dismissive, patients can request a different clinician or seek second opinions. Advocacy groups and online communities (like those for rare diseases) often provide scripts and tips for navigating difficult conversations.
Q: Is patient-centred communication just about being nice?
No—it’s about being effective. While empathy and kindness are important, patient-centred communication is rooted in evidence. Research shows that patients who feel respected are more likely to disclose critical information, adhere to treatments, and have better long-term outcomes. It’s not about avoiding tough conversations; it’s about framing them in a way that respects the patient’s autonomy and reduces fear. For example, breaking bad news with phrases like "I’m here to support you" instead of "You have X condition" can make the conversation more manageable.
