
Where It All Began
The origins of the medical office as we recognize it today are rooted in the 19th century, when urbanization and the rise of germ theory forced a reckoning with how medicine was delivered. Before then, doctors made house calls, treating patients in their homes or small rented spaces. But as cities grew, so did the demand for centralized care. The first true medical offices emerged in the late 1800s—not as grand institutions, but as modest rooms above apothecaries or in converted storefronts. These spaces were functional, not inviting. A single exam table, a shelf of glass jars labeled with Latin names, and a ledger for tracking payments. The focus was on the doctor’s expertise, not the patient’s experience. The real turning point came with the Flexner Report of 1910, which standardized medical education and elevated the status of physicians. Suddenly, medical offices weren’t just backdrops for healing—they were extensions of the doctor’s authority. The design reflected this: larger waiting areas to impress patients, private consultation rooms to maintain professionalism, and filing cabinets to organize the growing mountain of patient records. By the 1920s, the medical office had become a symbol of modernity, even as it remained a place where the doctor’s word was law and the patient’s role was largely passive. The space itself reinforced hierarchy—literally. Doctors sat at desks elevated above reception areas, and exam rooms were designed so patients had to look up to address them.The Early Signs
The cracks in this model began to show in the 1940s, as insurance companies started paying for care. For the first time, medical offices had to justify their existence not just as places of healing, but as businesses. The shift was subtle at first: a second phone line for billing inquiries, a separate ledger for insurance claims. But it marked the beginning of a slow transformation. By the 1950s, the medical office was no longer just a doctor’s domain—it was a shared space where nurses, medical assistants, and eventually administrative staff all played roles. The layout had to accommodate this. Reception areas expanded to handle more patients, and exam rooms were repurposed for procedures that couldn’t be done in hospitals. The real inflection point came with the introduction of electronic health records (EHRs) in the 1970s. Suddenly, the medical office wasn’t just a physical space—it was a node in a network. The hum of the copy machine Whitmore remembered gave way to the clatter of keyboards as doctors began typing notes into systems. This wasn’t just a technological upgrade; it was a philosophical one. The medical office could no longer be just a place where doctors dictated orders. It had to be a place where data flowed seamlessly, where every interaction could be tracked, audited, and billed. The patient, once the center of the experience, now had to navigate a system designed for efficiency over empathy.The Turning Point
The moment the medical office became unrecognizable from its 19th-century roots arrived in the 1990s, when two forces collided: the rise of managed care and the internet. Managed care companies, desperate to control costs, began dictating how medical offices operated. Pre-authorization forms piled up. Denial letters became a daily reality. The office that had once been a doctor’s personal domain now had to answer to insurers, government regulators, and corporate overlords. Meanwhile, the internet was democratizing information. Patients who once deferred to their doctors’ authority now Googled symptoms before entering the exam room. The medical office couldn’t ignore this shift—it had to adapt or risk becoming obsolete. The turning point wasn’t just about technology, though. It was about the physical space itself. Architects and healthcare designers began rethinking medical offices as environments that could reduce anxiety, improve flow, and even boost revenue. Waiting rooms were redesigned to feel less like holding cells and more like extensions of patients’ homes. Exam rooms got wider, with built-in sinks and storage for patient belongings. The reception desk, once a barrier, became a hub for patient engagement. And for the first time, the medical office was being treated as more than just a place to see patients—it was being treated as an experience."The office isn’t just where care happens; it’s where trust is built—or broken." —Dr. Richard Chen, former president of the American Academy of Family Physicians
The Build-Up, Year by Year
| Period | What Changed |
|---|---|
| 1890s–1920s | Shift from home visits to centralized medical offices; standardized layouts with exam rooms and waiting areas. Doctors’ authority reinforced through space design (elevated desks, formal consultations). |
| 1940s–1960s | Insurance payments introduce billing systems; medical offices hire administrative staff. Layouts expand to include separate areas for charting and phone calls. First use of color psychology (soothing blues/greens) in waiting rooms. |
| 1970s–1980s | EHRs emerge; medical offices adopt typewriters and early computers. HIPAA precursors require secure record-keeping. Open-bay designs tested (later abandoned due to patient privacy concerns). |
| 1990s–2000s | Managed care forces medical offices to prioritize efficiency. Patient portals introduced; waiting rooms get televisions and Wi-Fi. "Patient-centered design" becomes a buzzword—though implementation varies wildly. |
| 2010s–Present | Telehealth integrates into medical offices; hybrid models emerge (in-person + virtual visits). AI-driven scheduling and predictive analytics optimize workflows. "Wellness centers" rebrand medical offices as lifestyle hubs. |
Lessons From the Journey
- The office reflects power dynamics. From elevated desks to open-bay failures, every design choice reinforces who holds authority—doctors, insurers, or patients.
- Technology doesn’t replace human touch—it reshapes it. EHRs made medical offices more efficient but also more impersonal unless actively countered.
- Compliance is the silent architect. HIPAA, CMS regulations, and insurance requirements dictate layouts long before aesthetics do.
- The patient experience is the last frontier. Despite decades of redesign, medical offices still struggle to balance efficiency with empathy.
Where Things Stand Today
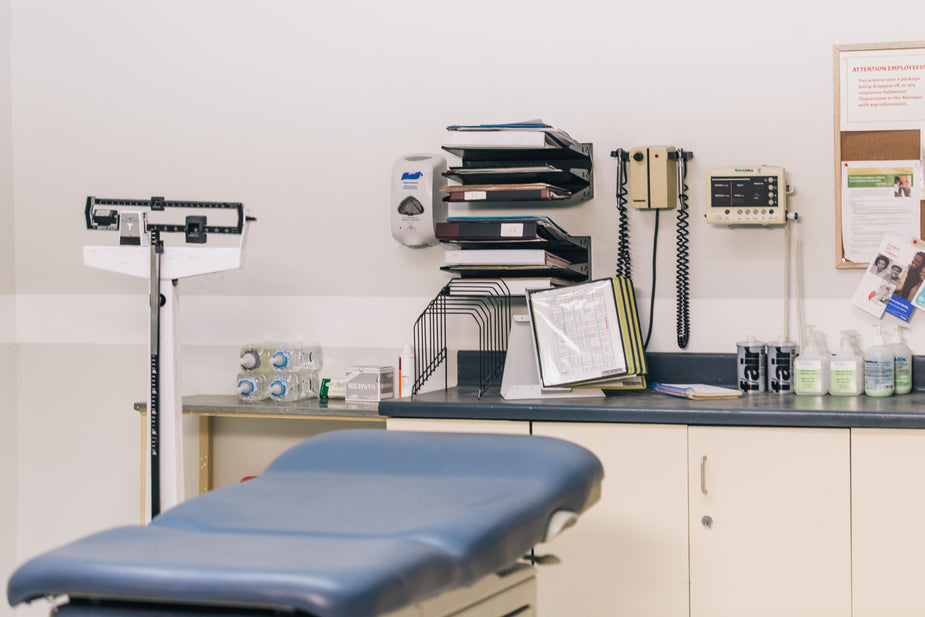
If you walked into a medical office in 2024, you’d find a space that’s both familiar and alien. The waiting room might offer free coffee and charging stations, but the check-in process still requires jumping through hoops for insurance verification. Exam rooms are equipped with high-definition monitors for telehealth, yet the doctor’s note might still be dictated into a voice-to-text system that occasionally mishears "aspirin" as "insulin." The receptionist’s role has expanded to include patient advocate, tech troubleshooter, and emotional support—all while fielding calls from insurers. What hasn’t changed is the fundamental tension at the heart of what is a medical office: it’s a place where healing and bureaucracy collide. The best modern medical offices have found ways to soften that collision. They use color and lighting to reduce stress, train staff to listen more than they speak, and design workflows that minimize patient friction. But the underlying challenge remains: how to make a space that’s both a business and a sanctuary. The answer isn’t in the furniture—it’s in the people who occupy it and the systems they navigate.
Conclusion
The evolution of the medical office is a story of unintended consequences. Each innovation—from the Flexner Report to EHRs to telehealth—was meant to improve care, but often ended up complicating it. The office itself became a metaphor for healthcare: a system that values efficiency over humanity, but still clings to the hope that it can do both. Dr. Whitmore’s old office, with its buzzing lights and sobbing patients, wasn’t a relic of the past—it was a warning. The medical office will always be more than four walls. It’s a reflection of what society prioritizes in healthcare: speed, cost, or the patient’s well-being. The question now isn’t just what is a medical office, but what it could become. As technology blurs the lines between in-person and virtual care, the physical medical office might shrink—or it might transform into something entirely new. Perhaps it will become a community hub, where primary care, mental health, and social services converge. Or maybe it will dissolve into a network of micro-clinics, each optimized for a single specialty. One thing is certain: the office will continue to adapt, not because it wants to, but because it has to. And in that adaptation lies the story of healthcare itself.Comprehensive FAQs
Q: What’s the difference between a medical office and a clinic?
A: The terms are often used interchangeably, but medical offices typically refer to single-practitioner or small-group settings (e.g., a solo family doctor’s practice), while clinics are larger, multi-specialty facilities. Clinics often employ more staff, handle higher patient volumes, and may offer extended services like labs or imaging. A medical office is more likely to be doctor-centric, whereas clinics can be institution-driven (e.g., hospital-owned).
Q: How much does it cost to set up a medical office?
A: Costs vary widely based on location, size, and whether the space is leased or purchased. A basic medical office in a suburban area might require an initial investment of $100,000–$500,000 for leasehold improvements, equipment, and compliance upgrades (e.g., HIPAA-secure networks). Urban or specialty practices (e.g., cardiology) can exceed $1 million, especially if they include procedural rooms. Leasing alone can range from $2–$10 per square foot monthly, depending on the market.
Q: What’s the most important feature of a medical office layout?
A: Patient flow. The best-designed medical offices prioritize a logical sequence: check-in → consultation → exam → checkout, with minimal backtracking. Other critical elements include private exam rooms (to preserve dignity), ergonomic workstations for staff, and secure storage for PHI. The reception area should be visible from the waiting room to reduce anxiety, while exam rooms should have easy access to utilities (e.g., sinks, electrical outlets for medical devices).
Q: How do medical offices handle patient privacy?
A: Compliance with HIPAA and state laws is non-negotiable. Medical offices use a mix of physical and digital safeguards: locked filing cabinets for paper records, encrypted EHR systems, and strict access controls (e.g., biometric scanners for storage rooms). Staff training is mandatory, covering everything from not discussing patient info in public to securing mobile devices. Some offices even use "white noise" machines in waiting areas to prevent overheard conversations. Breaches can result in fines up to $1.5 million per violation, making privacy a top priority.
Q: Can a medical office operate without electronic health records (EHRs)?
A: Technically, yes—but it’s increasingly impractical. While some small practices still use paper charts, most medical offices rely on EHRs for billing, compliance, and interoperability. The Centers for Medicare & Medicaid Services (CMS) has phased out paper-based incentive programs, and many insurers now require electronic claims submissions. That said, hybrid models (e.g., EHRs for billing but paper for notes) exist, though they introduce inefficiencies. The real question isn’t can you operate without EHRs, but how well can you compete without them.
Q: What’s the biggest challenge facing medical offices today?
A: Staffing shortages and burnout. The pandemic exacerbated a long-standing crisis: medical offices struggle to hire and retain nurses, medical assistants, and even front-desk staff. According to the American Medical Association, nearly 60% of physicians report burnout, often linked to administrative burdens in the office. Compounding this is the rise of corporate medicine—larger health systems absorbing smaller medical offices, which can strip away the autonomy and community ties that once defined independent practices.
