
Where It All Began
West Virginia’s struggle with depression didn’t start with the opioid epidemic or the coal bust. It went back further—to the decline of manufacturing in the 1980s and the slow bleed of opportunity that followed. When factories closed and mines scaled back, entire towns lost their economic lifelines. The state’s poverty rate, already high, climbed steadily. By the 1990s, rural hospitals were shutting down, leaving residents with few options for primary care, let alone mental health services. The isolation was palpable. In counties where the nearest psychologist was an hour’s drive away, people learned to suffer in silence. The early signs were subtle but unmistakable. In the late 1990s, suicide rates began to creep upward, particularly among middle-aged men. Researchers later linked this to what they called "deaths of despair"—a term that would later define the crisis in the state with the highest depression rate. These weren’t dramatic, headline-grabbing tragedies. They were quiet, often overlooked: a farmer hanging himself in his barn, a nurse overdosing in her bathroom, a retired teacher drinking herself to sleep every night. The common thread? A lack of purpose, a sense of being forgotten, and no one to turn to.The Early Signs
What made West Virginia different wasn’t just the economic hardship but the way it compounded. The state’s geography—mountains and valleys that made travel difficult—exacerbated the problem. Mental health professionals were concentrated in cities like Charleston and Morgantown, leaving vast stretches of the state underserved. Meanwhile, the cultural narrative around depression was one of weakness. "You just gotta tough it out," was the refrain. Even today, many West Virginians hesitate to admit they’re struggling, fearing judgment or being labeled "crazy." The opioid crisis, which surged in the 2000s, didn’t just add to the depression rates—it became a feedback loop. Painkiller addiction led to financial ruin, broken families, and, for some, a desperate turn to heroin when prescriptions dried up. The cycle of addiction and despair deepened, and with it, the stigma around seeking help. By the time the state’s depression rates spiked in the late 2010s, the damage was already entrenched. The state with the highest depression rate wasn’t just a statistic; it was a symptom of a society left to rot.The Turning Point
The moment West Virginia’s mental health crisis became undeniable was in 2016, when the state’s suicide rate surpassed its national average by nearly 30%. That year, Governor Jim Justice—who’d once owned a coal company—declared a state of emergency over the opioid epidemic. But the move was too little, too late for many. The real turning point came when local nonprofits and grassroots organizations began pushing for systemic change. They argued that treating depression required more than just rehab centers; it needed economic revitalization, better healthcare access, and a cultural shift in how mental illness was perceived. The push gained traction when data revealed that West Virginia’s depression rates were being driven by a perfect storm: unemployment, opioid addiction, and a lack of social support. For the first time, policymakers had to confront the reality that their state wasn’t just struggling—it was in freefall. The state with the highest depression rate had become a cautionary tale, a warning of what happens when a region’s identity is tied to dying industries and its people are left with no safety net."West Virginia didn’t become the depression capital of America overnight. It took decades of neglect, but the difference between survival and collapse is often just a matter of when help arrives. For us, that help came too late for some." — Dr. Rachel Whitaker, Behavioral Health Director, West Virginia Department of Health
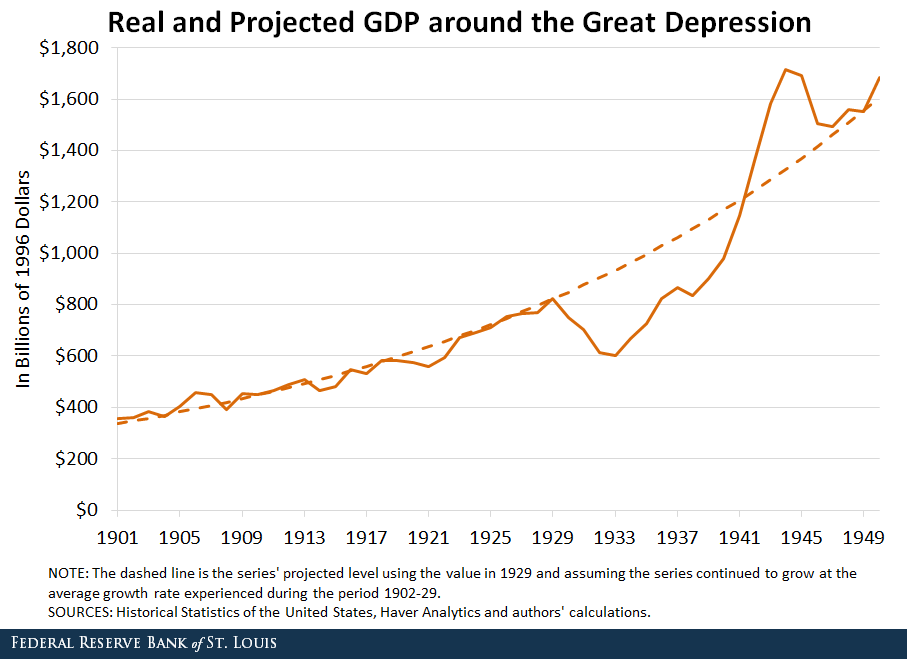
The Build-Up, Year by Year
| Period | What Happened / What Changed | |------------------|---------------------------------------------------------------------------------------------------------------------------------------------------------------------------------------------------------------------------------| | 2008–2012 | Coal industry employment drops by 25%. Rural hospitals close, leaving counties with no mental health services. Suicide rates begin rising, particularly in Appalachian regions. Opioid prescriptions peak. | | 2013–2017 | Opioid-related deaths triple. State declares emergency in 2016, but funding for treatment remains insufficient. Depression rates climb as addiction and economic despair intertwine. First community-based mental health programs emerge. | | 2018–Present | West Virginia’s depression rate hits 19.3%—nearly double the national average. State expands Medicaid, increasing access to therapy, but waitlists remain long. Grassroots initiatives focus on stigma reduction and peer support networks. |Lessons From the Journey
- Economic decline and mental health are inextricably linked. When industries collapse, entire communities lose their sense of purpose—and without purpose, depression thrives. - Stigma is the silent killer. In West Virginia, asking for help was long seen as a sign of weakness. Breaking that stigma required more than policy; it needed storytelling and community leaders speaking out. - Opioids didn’t cause the crisis, but they accelerated it. The epidemic exposed existing vulnerabilities, turning individual struggles into a public health catastrophe. - Rural areas are the most underserved. The lack of infrastructure in remote counties means people often don’t seek help until it’s too late. - Small steps can make a difference. Programs like the West Virginia Prevention Research Center and local NAMI affiliates proved that even limited resources could create lifelines. - Cultural identity matters. West Virginians take pride in their resilience, but resilience has limits. Acknowledging that was the first step toward healing.Where Things Stand Today
As of 2024, West Virginia remains the state with the highest depression rate in the U.S., though the numbers have stabilized slightly—thanks in part to expanded Medicaid, increased funding for mental health services, and community-led initiatives. The state now has more therapists and counselors than it did a decade ago, but demand still outstrips supply. In some counties, waitlists for therapy exceed six months. The opioid crisis has eased slightly, but the scars remain: addiction rates are still high, and the economic recovery has been uneven. What’s changed is the conversation. Where silence once reigned, there’s now a growing acknowledgment that depression is not a personal failure but a public health issue. Organizations like The Hope Center in Charleston offer free counseling, and schools are integrating mental health education earlier. Yet challenges persist. The state’s aging population means more seniors struggling with isolation, while young adults face job scarcity and the lingering effects of the opioid epidemic. The road to recovery is long, but for the first time, there’s a path—and people are walking it, one step at a time.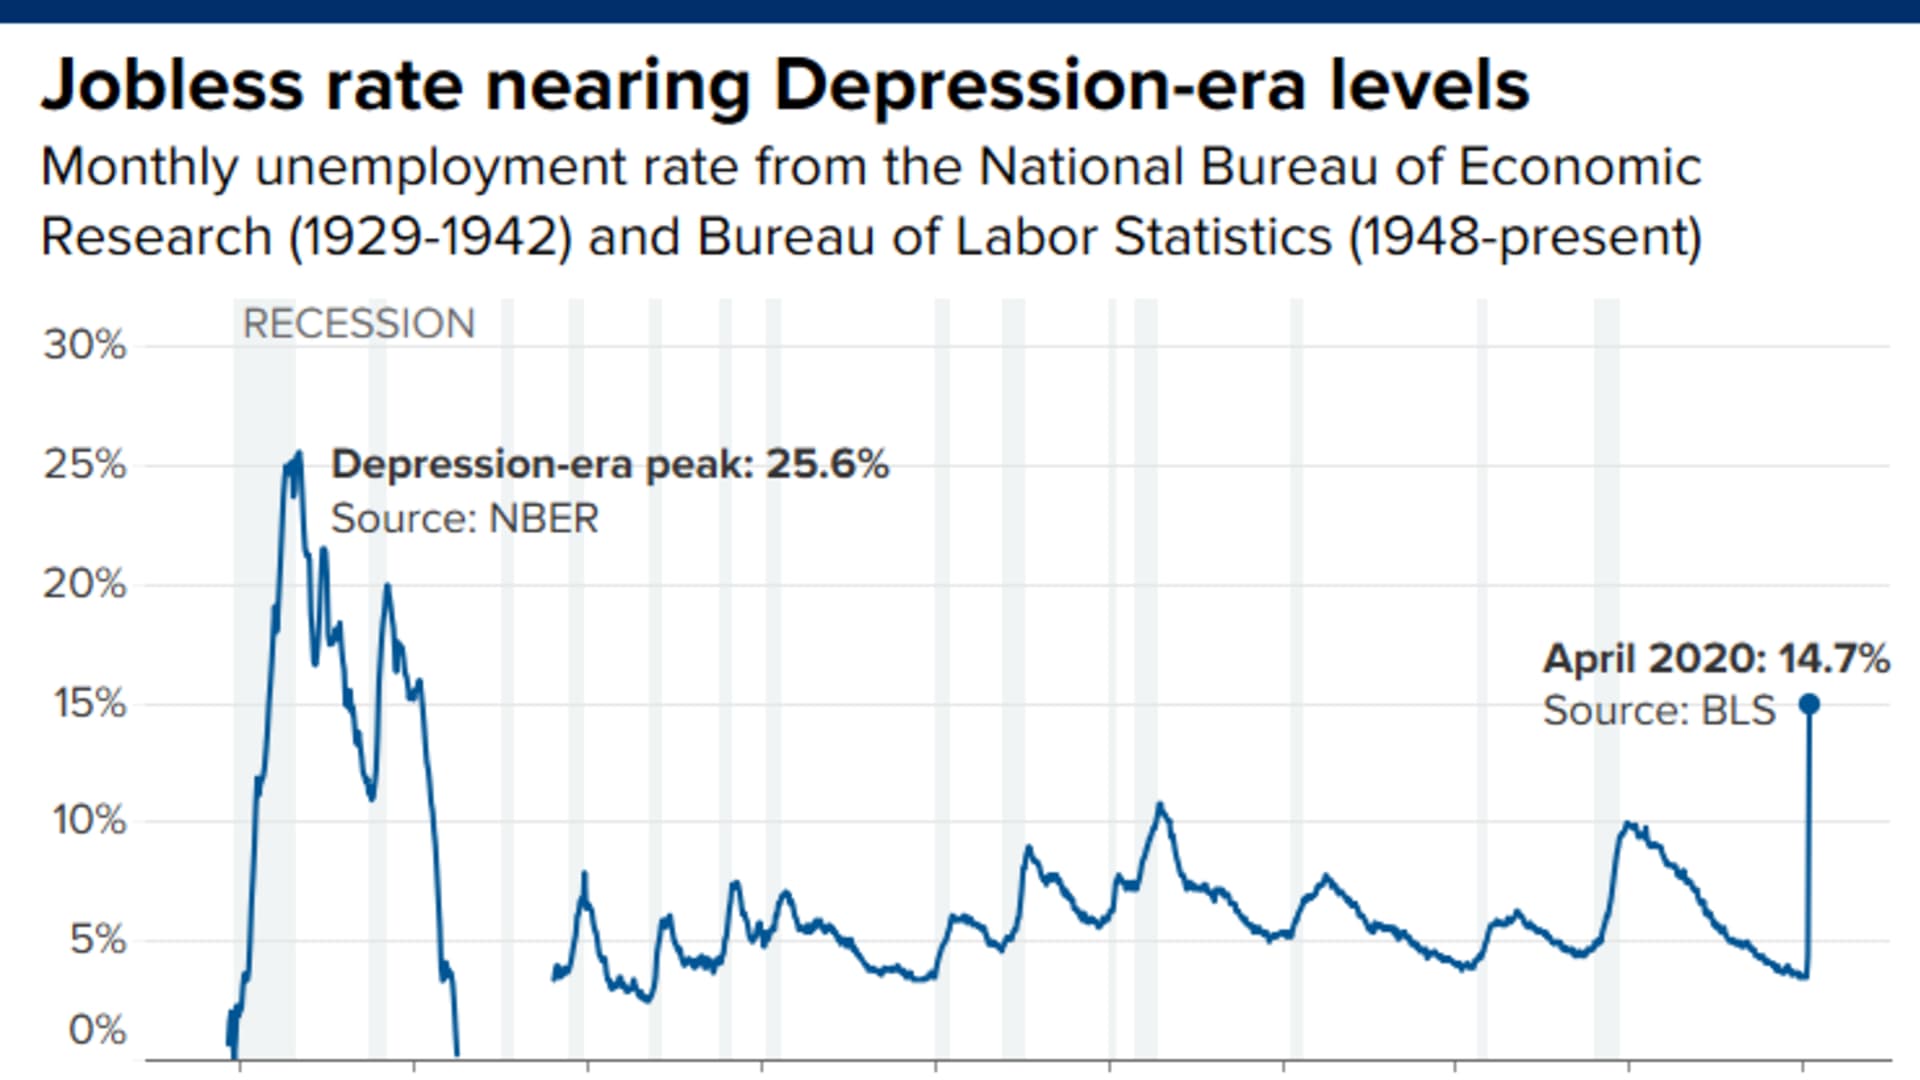
Conclusion
West Virginia’s story is more than a cautionary tale about economic decline or drug addiction. It’s a testament to what happens when a society’s wounds go untreated for too long. The state with the highest depression rate didn’t become that way by accident. It was the result of decades of neglect, a refusal to see mental health as a priority, and a culture that valued toughness over vulnerability. But it’s also a story of resilience. Despite everything, West Virginians are fighting back—not just with policy changes, but with compassion, with community, and with the quiet determination to rewrite their narrative. The lessons from West Virginia are clear: mental health crises don’t exist in isolation. They’re tied to economics, to geography, to culture. And they demand solutions that are as comprehensive as the problems they address. The state’s journey isn’t over, but the fact that it’s even having this conversation is progress. For the millions of Americans watching, it’s a reminder that depression doesn’t discriminate—and neither should the fight against it.Comprehensive FAQs
Q: Why does West Virginia have such high depression rates?
West Virginia’s depression crisis is driven by a combination of economic decline (particularly in coal), the opioid epidemic, lack of healthcare access in rural areas, and deep-seated stigma around mental illness. The state’s poverty rate, isolation, and cultural attitudes toward seeking help all contribute to the problem.
Q: Has the depression rate in West Virginia improved recently?
While the rate has stabilized slightly due to expanded Medicaid and mental health programs, West Virginia still ranks as the state with the highest depression rate in the U.S. Progress is being made, but challenges like long therapy waitlists and economic struggles persist.
Q: What’s being done to address the crisis?
Efforts include expanding Medicaid, funding community mental health programs, reducing opioid prescriptions, and launching stigma-reduction campaigns. Grassroots organizations also play a key role in providing free counseling and peer support.
Q: Are other states at risk of the same crisis?
Yes. States with high poverty rates, declining industries, and opioid struggles—like Kentucky, Ohio, and Pennsylvania—face similar risks. West Virginia’s experience serves as a warning about the dangers of neglecting mental health infrastructure.
Q: How can someone in West Virginia get help if they’re struggling?
Resources include the West Virginia Crisis Line (1-800-274-TALK), local NAMI affiliates, and community health centers. Medicaid expansion has increased access to therapy, though waitlists can still be long in some areas.
Q: Is West Virginia’s depression rate higher than during the opioid peak?
While opioid-related deaths have decreased slightly, depression rates remain elevated due to long-term economic and social factors. The crisis has evolved but hasn’t disappeared.
Q: What’s the biggest misconception about West Virginia’s mental health crisis?
The biggest myth is that it’s solely an opioid problem. While addiction is a major factor, the root causes are economic, cultural, and systemic. Depression in West Virginia is as much about lost jobs and broken communities as it is about pills.
