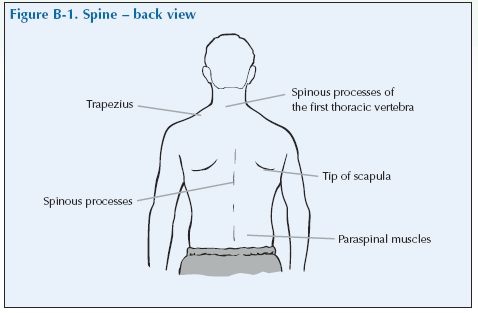
Common Myths About the Small of the Back
The lumbar region is a magnet for misinformation, from wellness trends to outdated medical advice. Many assume that pain here is inevitable with age or that stretching alone can fix structural issues. Others blame "bad energy" or "toxins" without acknowledging the role of muscle imbalances or spinal alignment. These oversimplifications obscure the real culprits: repetitive stress, weak core stability, and the way we distribute weight—whether from heavy bags, poor footwear, or years of slouching. The confusion persists because the small of the back is both resilient and fragile. It can handle immense loads when supported correctly, but a single awkward lift or prolonged poor posture can trigger a cascade of problems. The myths aren’t harmless—they delay proper treatment and reinforce habits that worsen conditions like herniated discs or degenerative disc disease.Myth 1: "You’re too old for that—back pain is just part of aging."
Age does increase the risk of lumbar issues, but chronic pain isn’t an automatic sentence. Degenerative changes—like thinning discs or bone spurs—are common after 40, but they don’t always cause pain. Many elderly individuals move with ease because they’ve maintained core strength, flexibility, and proper biomechanics. The small of the back degenerates when it’s neglected, not just because of time. Research shows that only about 20% of people over 60 with spinal degeneration report significant pain. The rest adapt through movement, strength training, and ergonomic adjustments. The myth ignores the fact that lifestyle choices—like regular exercise or avoiding prolonged sitting—can mitigate age-related decline. Pain in the small of the back isn’t a badge of aging; it’s a call to reassess how you’re using your body.Myth 2: "Sleeping on your stomach is harmless—it’s just a matter of preference."
This is one of the most damaging misconceptions about lumbar health. Sleeping face-down forces the spine into a twisted position, hyper-extending the small of the back while rotating the neck. Over time, this strains the lower vertebrae, tightens hip flexors, and can even contribute to disc herniation. The myth persists because discomfort might not appear immediately, but the cumulative effect is real. Experts recommend side sleeping or back sleeping with support to maintain spinal alignment. The small of the back thrives when it’s in a neutral position, not contorted. If you’ve slept on your stomach for decades, transitioning gradually with a pillow under the pelvis can help, but the habit itself is a silent contributor to chronic tension.Myth 3: "If it hurts, you should rest it completely until the pain goes away."
This advice, often given for acute back pain, can backfire. Prolonged inactivity weakens the muscles supporting the lumbar region, making it more prone to future injuries. The small of the back needs controlled movement—not immobilization—to heal. Gentle walking, core exercises, and avoiding heavy lifting for a short period are far more effective than bed rest. Studies show that patients who resume light activity within 48 hours of onset recover faster than those who stay sedentary. The key is avoiding movements that aggravate the pain while gradually rebuilding strength. The myth of "rest until it’s gone" ignores the body’s need for motion to repair itself.
What Holds Up to Scrutiny
At the core, the small of the back’s health hinges on three pillars: mechanical load management, muscle balance, and spinal mobility. The lumbar spine isn’t designed to bear heavy loads in isolation—it relies on the pelvis, hips, and core to distribute force. When these areas weaken, the small of the back compensates, leading to pain. The good news? This means prevention and treatment are within reach for most people. The most reliable evidence points to strength training for the posterior chain (hamstrings, glutes, lower back) and core stability exercises as the best defenses. Poor posture—whether from desk jobs, smartphones, or ill-fitting shoes—is another verified risk factor. The small of the back isn’t just a passive structure; it’s a dynamic system that adapts to how we use it."The lumbar spine is a canary in the coal mine for overall movement quality. If it’s hurting, it’s often telling you that something else—like weak glutes or tight hip flexors—is off balance." — Dr. Stuart McGill, PhD, Professor Emeritus of Spinal Biomechanics
| Common Belief | What the Evidence Says |
|---|---|
| "Lifting with your back is safer than bending your knees." | Incorrect. The small of the back is most stable when the hips and knees are bent, keeping the load close to the body. "Back lifting" increases intra-abdominal pressure but also strains the lumbar discs over time. |
| "Chiropractic adjustments are the only way to fix a slipped disc." | Not true. While adjustments may provide temporary relief, 90% of herniated discs heal on their own with rest, physical therapy, and core strengthening. Surgery is rarely needed unless there’s nerve compression. |
| "High heels are bad for your back, but flats are fine." | Both extremes are problematic. High heels alter pelvic tilt, increasing lumbar strain. Flat shoes lack shock absorption, leading to overuse injuries. A 1–2 inch heel with arch support is often the safest compromise. |
| "You need expensive equipment to strengthen your core." | False. Bodyweight exercises like dead bugs, bird dogs, and planks (when done correctly) are highly effective. The small of the back benefits more from consistent, low-impact movement than from gym machinery. |
Why the Confusion Persists
The small of the back is a moving target—literally. Its health depends on a chain reaction of factors: how you sit, how you lift, how you breathe, even how you sleep. This complexity makes it easy to blame symptoms on a single cause (e.g., "my mattress is bad") while ignoring the bigger picture. Social media and wellness influencers often oversimplify solutions, promoting quick fixes like "back braces" or "magic stretches" without addressing root imbalances. Another obstacle is the lack of standardized advice. A physiotherapist might prescribe one approach, while a chiropractor offers another, leaving patients confused about which path to follow. The small of the back doesn’t respond to one-size-fits-all solutions—it demands personalized attention to movement patterns, ergonomics, and lifestyle. Until the public understands this, myths will keep circulating, and so will the pain.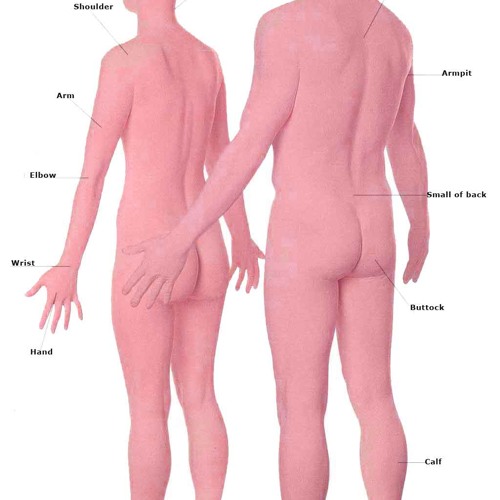
Conclusion
The small of the back is more than a source of discomfort—it’s a reflection of how we move through the world. Ignoring it leads to chronic issues; nurturing it with smart habits can prevent years of agony. The key isn’t avoiding all activity or chasing the latest back-pain cure. It’s about rebuilding balance: strengthening the muscles that support the lumbar spine, correcting posture before it becomes ingrained, and recognizing that the small of the back doesn’t fail in isolation. If you’ve spent years slouching, lifting poorly, or dismissing twinges as "just part of life," the good news is that change is possible. Start small: swap the couch for a standing desk, invest in shoes with proper arch support, or try a 10-minute daily core routine. The small of the back doesn’t need a miracle—it needs consistent, intentional care.Comprehensive FAQs
Q: Can sitting at a desk all day permanently damage the small of the back?
A: Not permanently, but prolonged sitting weakens the muscles that stabilize the lumbar spine, increasing the risk of disc degeneration and herniation over time. The solution isn’t to sit upright rigidly—it’s to move frequently, use a chair with lumbar support, and take micro-breaks every 30 minutes to stretch or walk. Standing desks help, but only if they encourage better posture, not just a different kind of strain.
Q: Is it true that walking is the best exercise for back pain?
A: Walking is excellent for low-impact mobility and circulation, but it’s not a cure-all. The small of the back benefits more from strengthening exercises (like glute bridges or deadlifts with proper form) and flexibility work (such as cat-cow stretches or pigeon pose). A balanced routine combines cardio, core stability, and controlled movement to address pain holistically.
Q: How do I know if my back pain is serious enough to see a doctor?
A: Seek medical attention if pain radiates down the legs (possible sciatica), causes numbness/tingling, or follows a traumatic injury. Red flags also include loss of bladder/bowel control (a medical emergency) or pain that worsens at night. For most cases, however, physical therapy or a sports medicine specialist can provide targeted solutions before surgery becomes necessary.
Q: Can yoga really help the small of the back, or is it just a fad?
A: Yoga can be highly beneficial if practiced correctly—especially styles like Iyengar or Vinyasa, which emphasize alignment. Poses like child’s pose, cobra, and seated forward folds stretch the lumbar region safely. However, overdoing twists or deep backbends without core strength can exacerbate issues. The best approach is to work with a qualified instructor who understands spinal biomechanics.
Q: Why does my small of the back hurt more in the morning?
A: Morning stiffness is often due to fluid buildup in the discs (which rehydrate overnight) or tightened muscles from prolonged inactivity. Poor sleep posture, an unsupportive mattress, or even stress-induced muscle tension can also play a role. Try gentle movement first thing (like a short walk or cat-cow stretches) to lubricate the spine before jumping into activity.
Q: Are there foods that can reduce inflammation in the small of the back?
A: While diet isn’t a direct fix, anti-inflammatory foods (fatty fish, leafy greens, turmeric, berries) may help reduce systemic inflammation that contributes to joint and disc discomfort. Conversely, processed sugars, trans fats, and excessive alcohol can worsen inflammation. Hydration is also key—dehydration reduces disc elasticity, increasing strain on the lumbar spine.
Q: How long does it take to strengthen the small of the back?
A: Results vary, but consistent, targeted exercise (2–3 times per week) can show improvements in 4–12 weeks, depending on the individual’s starting point. The small of the back responds best to progressive overload—gradually increasing strength and mobility over time. Patience is critical; rushing can lead to setbacks. Track progress with a physical therapist or trainer for personalized guidance.
