
Common Myths About the RNA Program
The RNA program’s promise has spawned a cottage industry of oversimplifications. One persistent narrative frames it as a silver bullet for all diseases, while another dismisses it as nothing more than a pandemic-era fluke. These extremes obscure the nuanced reality: RNA-based tools are powerful but not omnipotent, with distinct strengths and limitations. The confusion stems partly from how the term itself is used—sometimes to describe mRNA vaccines, other times to encompass broader genetic engineering. Without clear boundaries, even well-intentioned discussions devolve into hype or skepticism. Another layer of misunderstanding arises from the field’s rapid pace. What was cutting-edge five years ago—like lipid nanoparticle delivery systems—is now a standard component of approved therapies. Meanwhile, experimental techniques, such as self-amplifying RNA or prime-boost vaccination strategies, remain in early-stage trials. The result? A moving target where yesterday’s breakthrough becomes today’s speculative technology.Myth 1: The RNA program is just about mRNA vaccines
The association between the RNA program and mRNA vaccines is understandable, given their high-profile success. Vaccines like Pfizer-BioNTech’s and Moderna’s demonstrated that mRNA could safely instruct cells to produce protective antigens, a feat once considered improbable. Yet this narrow focus overlooks the broader scope of RNA-based interventions. Therapeutic applications—such as siRNA drugs for genetic disorders or CRISPR-guided RNA for gene editing—operate on entirely different principles. Even within vaccines, the RNA program includes self-replicating RNA, DNA-primed RNA, and multivalent RNA designs, each with distinct mechanisms and trade-offs. The confusion persists because mRNA vaccines dominated public discourse during the pandemic, eclipsing other RNA applications. For instance, Alnylam’s Onpattro, an FDA-approved siRNA therapy for hereditary transthyretin amyloidosis, has been treating patients since 2018—long before COVID-19. Similarly, RNA interference (RNAi) platforms are being tested for Huntington’s disease and liver conditions, proving that RNA’s utility extends far beyond infectious diseases. The RNA program’s diversity means its impact isn’t limited to one domain; it’s a toolkit with multiple tools, each suited to different challenges.Myth 2: RNA therapies are inherently unsafe
The safety of RNA-based interventions is a legitimate concern, but it’s often framed in absolute terms. Early skepticism stemmed from RNA’s role in viral replication and its potential to trigger immune responses. However, decades of research—including clinical trials spanning over 40 years—have refined delivery methods and dosing strategies to mitigate risks. Lipid nanoparticles, for example, shield RNA from degradation and reduce off-target effects, a critical advancement that enabled mRNA vaccines. Regulatory agencies, including the FDA and EMA, have established rigorous guidelines for RNA therapeutics, requiring extensive preclinical and clinical data before approval. That said, risks aren’t nonexistent. Off-target effects, where RNA inadvertently alters unintended genes, remain a challenge in gene-editing applications. Immune responses to RNA can also limit repeat dosing, a hurdle for chronic conditions. Yet these issues are being addressed through chemical modifications (like pseudouridine in mRNA) and improved delivery systems. The key distinction is between theoretical risks and real-world outcomes. The RNA program’s safety profile is evolving, but it’s no longer the speculative gamble it once was.Myth 3: The RNA program will replace traditional gene therapy
RNA-based approaches are often pitched as a replacement for older gene therapy methods, such as viral vectors or plasmid DNA. While RNA offers advantages—like transient expression and reduced integration risks—it’s not a one-size-fits-all solution. Viral vectors, for instance, remain the gold standard for certain hereditary diseases where long-term gene expression is critical. RNA’s transient nature makes it ideal for vaccines or acute conditions but less suitable for lifelong treatments. The two modalities are complementary, not competitive: RNA excels in scenarios where temporary, controlled gene expression is desired, while viral vectors handle permanent corrections. The narrative of replacement also ignores the logistical realities. Developing an RNA therapy requires overcoming delivery challenges, such as targeting specific tissues or evading the immune system. Viral vectors, despite their risks, have a proven track record in delivering genes to difficult-to-reach cells. The RNA program’s strength lies in its flexibility, not its ability to obsolete existing methods. Hybrid approaches—combining RNA with other technologies—are already emerging, blending the best of both worlds.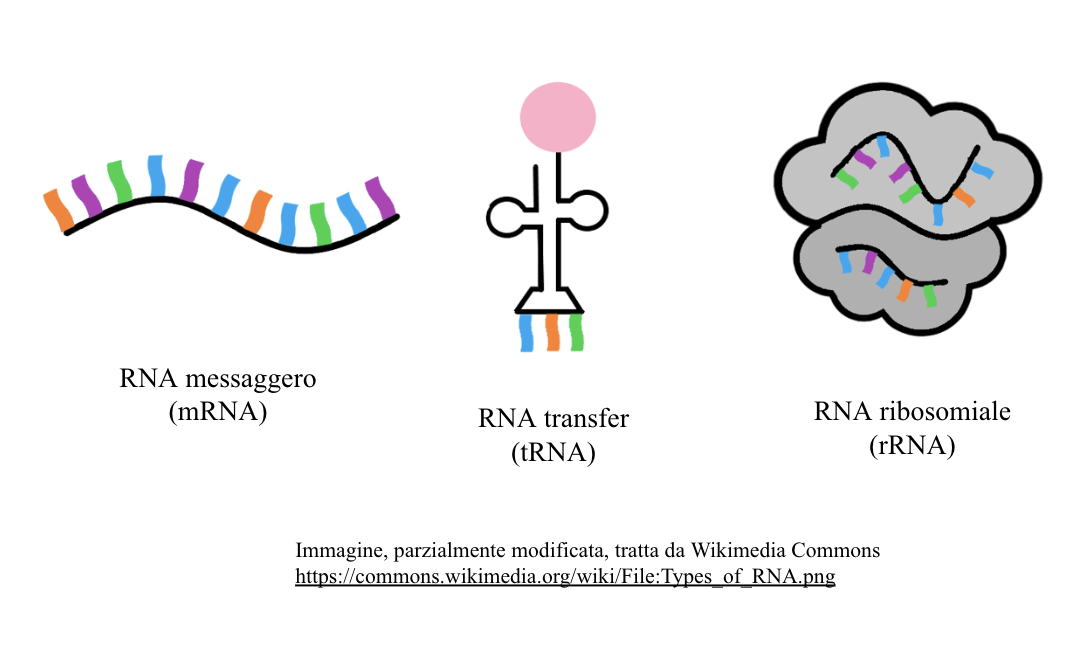
What Holds Up to Scrutiny
At its foundation, the RNA program rests on three verifiable pillars: mechanistic clarity, clinical validation, and industrial scalability. Mechanistically, RNA’s role as a genetic intermediary is well understood, with decades of structural biology underpinning its engineering. Clinical validation comes from approved therapies like Onpattro and vaccines that have administered billions of doses with demonstrated safety. Scalability, once a bottleneck, has improved with advances in synthetic biology and manufacturing—Moderna’s mRNA production, for example, now meets global demand without shortages. The field’s progress isn’t uniform, however. While mRNA vaccines have achieved near-universal recognition, other RNA applications face higher barriers. Gene-editing tools like CRISPR rely on RNA guides but require precise delivery to function, a challenge that persists despite recent breakthroughs. Similarly, siRNA therapies, though effective in lab settings, often struggle with in vivo stability. Yet the core premise—that RNA can be programmed to interact with biology in predictable ways—remains robust. The question isn’t whether the RNA program works, but how to refine its applications for specific diseases.“RNA is the missing link between DNA’s static instructions and the dynamic needs of the cell. By harnessing it, we’re not just treating symptoms—we’re rewriting the rules of therapy.” —Dr. Katalin Karikó, Nobel laureate and mRNA pioneer
| Common Belief | What the Evidence Says |
|---|---|
| RNA therapies are only for infectious diseases. | Approved siRNA drugs (e.g., Onpattro) treat genetic disorders, and RNA is being tested for cancer, rare diseases, and neurodegenerative conditions. |
| mRNA vaccines cause long-term genetic changes. | mRNA degrades quickly and doesn’t integrate into DNA; clinical data shows no evidence of genomic alterations. |
| RNA delivery is the biggest unsolved problem. | Lipid nanoparticles and other carriers have improved stability and targeting, though tissue-specific delivery remains an active research area. |
| The RNA program is a recent development. | RNA interference was discovered in 1998, and early mRNA work dates back to the 1980s—decades of foundational research precede today’s applications. |
| RNA therapies are too expensive to be practical. | Costs vary by application; while early RNA drugs are pricey, economies of scale (e.g., vaccine production) and competition are driving prices down. |
Why the Confusion Persists
The RNA program’s dual nature—as both a scientific discipline and a commercial juggernaut—fuels persistent confusion. On one hand, academic researchers treat it as a tool for basic biology, exploring RNA’s regulatory roles in diseases like Alzheimer’s or fibrosis. On the other, biotech firms market it as a platform for rapid drug development, with timelines measured in years rather than decades. This disconnect creates a gap between what’s theoretically possible and what’s clinically achievable. Media coverage often amplifies the hype, focusing on breakthroughs while downplaying the iterative nature of drug development. Another factor is the field’s interdisciplinary nature. RNA technologies intersect with chemistry, immunology, materials science, and computational biology, making it difficult for non-specialists to grasp the full picture. Even within the scientific community, collaboration between RNA engineers, clinicians, and regulatory experts is still evolving. Until these silos break down, misconceptions will persist—reinforced by oversimplified narratives that treat the RNA program as either a miracle cure or a fleeting trend.
Conclusion
The RNA program is neither a panacea nor a passing fad. Its trajectory is defined by incremental progress, where each approved therapy or published study builds on decades of foundational work. The mRNA vaccines were a proof of concept; the next phase will test RNA’s limits in chronic diseases, personalized medicine, and even agriculture. Yet for every success, there are setbacks—failed trials, immune responses, or delivery challenges—that remind us this is still a work in progress. What sets the RNA program apart is its adaptability. Unlike traditional drug development, which often targets proteins or small molecules, RNA allows for direct manipulation of genetic pathways. This flexibility is its greatest asset—and its biggest challenge. As the field matures, the distinction between “RNA as a tool” and “RNA as a paradigm” will sharpen. The goal isn’t to replace existing therapies but to expand the toolkit, offering new options for conditions once deemed untreatable.Comprehensive FAQs
Q: How does mRNA differ from DNA in therapeutic applications?
mRNA is a temporary messenger that instructs cells to produce proteins without altering DNA. Unlike DNA-based therapies (e.g., viral vectors), mRNA doesn’t integrate into the genome, reducing long-term risks. However, its transient nature limits its use to acute conditions or vaccines, where short-term expression is sufficient.
Q: Are RNA therapies safe for long-term use?
Current evidence suggests RNA therapies are safe for their intended durations, but long-term data is limited. mRNA vaccines, for example, have been monitored for over two years with no reports of genomic integration. For chronic conditions, repeated dosing may trigger immune responses, necessitating modifications like chemical stabilizations or alternative delivery methods.
Q: Can RNA be used to edit genes like CRISPR?
Yes, RNA is essential to CRISPR’s function—guide RNAs direct the Cas9 enzyme to specific DNA sequences. However, CRISPR-RNA systems face challenges in precision and off-target effects. Pure RNA-based editing (without proteins like Cas9) is also being explored, but these methods are still experimental.
Q: How long does it take to develop an RNA-based drug?
Timelines vary. mRNA vaccines were developed in under a year due to existing platforms and pandemic urgency. Most RNA therapeutics take 5–10 years from discovery to approval, similar to other biologics. Accelerated pathways (e.g., FDA’s mRNA vaccine guidelines) can shorten this for high-priority diseases.
Q: What are the biggest obstacles to widespread RNA therapy adoption?
The three primary hurdles are delivery (targeting specific tissues without immune rejection), stability (protecting RNA from degradation), and scalability (manufacturing consistent, high-quality batches). Advances in lipid nanoparticles and chemical modifications are addressing these, but each application requires tailored solutions.
Q: Are there non-medical uses for the RNA program?
Yes. RNA is being explored in agriculture (e.g., virus-resistant crops), biomanufacturing (programmable cell factories), and forensics (RNA-based diagnostics). Companies like Intellia are testing RNA therapies for livestock diseases, while synthetic biology startups use RNA to engineer microbes for sustainable materials.
Q: How do RNA vaccines compare to traditional vaccines?
RNA vaccines offer faster development and flexibility (e.g., rapid antigen updates), but traditional vaccines (live-attenuated or protein-subunit) often provide longer-lasting immunity. RNA’s strength lies in its speed and adaptability; its weakness is durability. Combination approaches (e.g., RNA prime + protein boost) may bridge this gap.
