5 Things Worth Knowing About Craniotomy vs Craniectomy
Understanding these procedures requires parsing their anatomical, physiological, and ethical dimensions. The choices aren’t made in isolation—they’re shaped by the patient’s age, the nature of the injury, and the surgeon’s institutional protocols. Below are the five most consequential factors in the debate over craniotomy vs craniectomy.1. The Primary Purpose: Pressure Relief vs. Tumor Removal
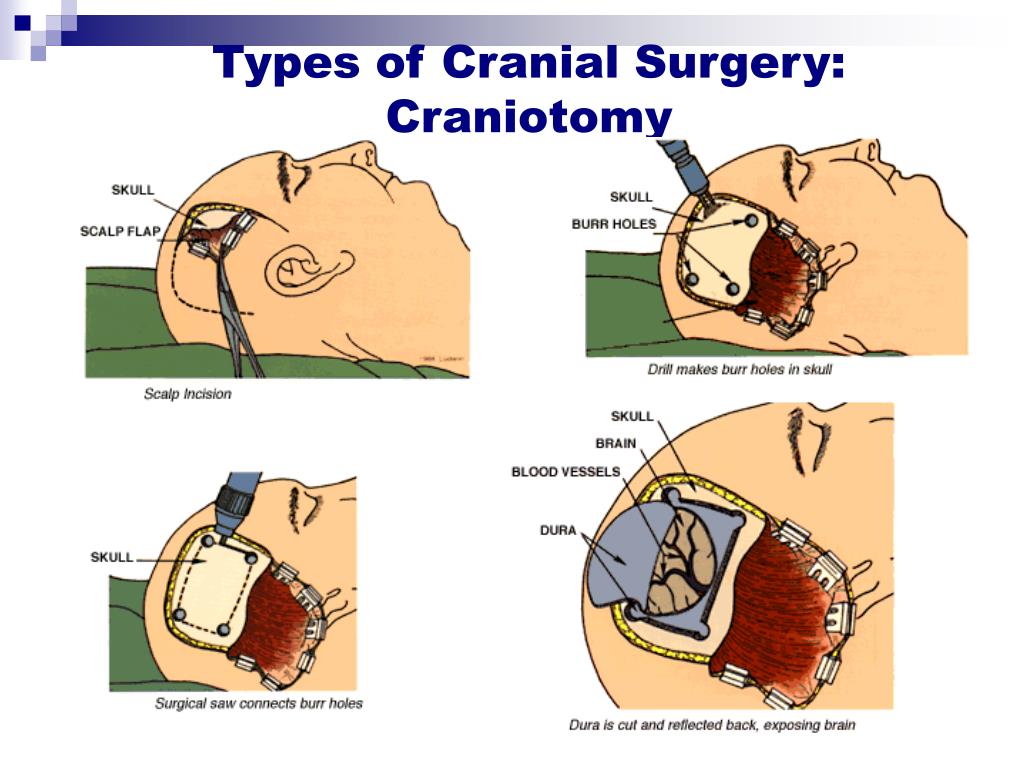
A craniotomy is fundamentally a containment procedure. Its primary goal is to provide controlled access to the brain for resection, biopsy, or clipping of aneurysms. The skull flap is removed temporarily, the surgery performed, and the bone replaced—often secured with titanium plates. This approach minimizes the risk of infection and preserves cranial integrity, but it assumes the brain can tolerate the procedure without swelling beyond its capacity. In contrast, a craniectomy is a decompression strategy. The bone flap is left off permanently to allow the brain to expand, reducing intracranial pressure (ICP) in cases of traumatic injury or stroke. The trade-off is immediate survival for potential long-term disability, including the need for a later cranioplasty (skull reconstruction). The decision often hinges on ICP thresholds. Neurosurgeons typically intervene when ICP exceeds 20–25 mmHg, a level that can trigger brainstem compression. A craniectomy may be the only option when a patient’s brain has swollen to the point where reattaching the skull would cause further damage. However, this comes with risks: the exposed brain is vulnerable to infection, and the absence of the skull can lead to complications like hydrocephalus or chronic subdural hematomas. Studies in Journal of Neurosurgery indicate that patients who undergo decompressive craniectomy for traumatic brain injury have a 20–30% higher mortality rate within six months compared to those who receive a craniotomy for similar conditions—though the survivors often have better immediate outcomes.2. The Role of Time: Emergency vs. Elective Surgery
Time is the most critical variable in craniotomy vs craniectomy decisions. A craniotomy is almost always an elective procedure—planned for tumor removal, aneurysm clipping, or vascular malformation repair. Patients are stabilized beforehand, and the surgery is scheduled when the team can operate with precision. A craniectomy, however, is almost always an emergency. When a patient arrives with a massive intracranial hemorrhage or diffuse axonal injury, the goal shifts from cure to stabilization. The surgeon must act within hours to prevent herniation, meaning there’s no time for extensive preoperative planning. This urgency explains why craniectomies are more common in trauma centers than in neurosurgical oncology units. The timing also affects outcomes. Elective craniotomies for tumors like gliomas have five-year survival rates that vary by malignancy grade, but they’re typically measured in decades for low-grade lesions. Decompressive craniectomies, by contrast, are assessed in terms of immediate survival and functional recovery. A 2018 meta-analysis in Critical Care Medicine found that while craniectomy improves survival in severe traumatic brain injury, only about 40% of survivors achieve a favorable neurological outcome (defined as a modified Rankin Scale score of ≤3). The discrepancy underscores how craniotomy vs craniectomy isn’t just about the procedure—it’s about the context in which it’s performed.3. The Long-Term Consequences: From Skull Reconstruction to Cognitive Decline
The immediate risks of craniotomy vs craniectomy are well-documented, but the long-term effects are often overlooked. A craniotomy patient may face complications like seizures, memory deficits, or motor weakness, but these are typically manageable with rehabilitation. A craniectomy patient, however, may require cranioplasty—a secondary procedure to replace the missing skull flap—anywhere from three months to two years later. This delay isn’t arbitrary: the brain must stabilize, and the patient must recover enough to tolerate another surgery. During this window, the exposed dura mater is at risk of infection, and the absence of the skull can lead to a syndrome called the "sinking skin flap," where the brain shifts downward, exacerbating neurological deficits. The cognitive toll can be profound. Patients who undergo decompressive craniectomy often experience executive dysfunction, language impairments, or even personality changes. A 2020 study in Neurology reported that 60% of survivors had persistent cognitive deficits at one year, compared to 30% of craniotomy patients. The reasons are multifaceted: prolonged brain swelling, ischemia from elevated ICP, and the physical trauma of decompression. Yet these risks are rarely discussed in preoperative consent forms, leaving families unprepared for the possibility of permanent disability. As one neurosurgeon told The New England Journal of Medicine, "The decision isn’t just about saving a life—it’s about what kind of life is being saved."4. The Ethical Dilemma: Quality of Life vs. Survival
The most contentious aspect of craniotomy vs craniectomy lies in the ethical gray area between prolonging life and preserving quality. In cases of severe traumatic brain injury, a craniectomy may be the only way to buy time, but it often results in patients who are awake but unable to speak, walk, or recognize loved ones. The question then becomes: at what point does survival cease to be meaningful? This dilemma is particularly acute in elderly patients or those with preexisting neurological conditions. Some institutions have adopted protocols where craniectomy is withheld if the patient’s prognosis is deemed poor, but these decisions are fraught with legal and moral complications. The ethical debate extends to resource allocation. Craniectomies are resource-intensive: they require ICU-level care, ventilatory support, and often long-term rehabilitation. In countries with strained healthcare systems, the choice between performing a craniectomy and allocating those resources elsewhere can become a silent policy. A 2019 paper in BMJ Open highlighted how hospitals in low-resource settings sometimes default to palliative care for patients who would otherwise receive a craniectomy in high-income nations. The result is a global disparity in craniotomy vs craniectomy outcomes, where geography—and not just medical science—determines survival.5. The Future: Advances in Monitoring and Minimally Invasive Options
Research into craniotomy vs craniectomy is increasingly focused on reducing the need for decompression in the first place. Real-time ICP monitoring, advanced imaging techniques, and osmotic therapies (like mannitol or hypertonic saline) have improved outcomes for patients who might have previously required a craniectomy. Some centers are exploring minimally invasive decompression—using endoscopic techniques or small burr holes to relieve pressure without full craniectomy. While these methods aren’t yet standard, they represent a shift toward less aggressive interventions. Another frontier is predictive modeling. Machine learning algorithms are being developed to predict which patients are most likely to benefit from a craniectomy versus those who might fare better with a craniotomy or medical management alone. Early results suggest that factors like age, initial GCS score, and the presence of midline shift can help tailor decisions. However, these tools are still in their infancy, and clinical judgment remains paramount. As one bioethicist noted, "No algorithm can replace the surgeon’s experience—but it can help frame the conversation in a way that’s more transparent for patients and families."
How These Facts Connect
The divide between craniotomy vs craniectomy isn’t just procedural—it’s philosophical. A craniotomy represents a surgical solution with a clear endpoint: access, treatment, and closure. A craniectomy, by contrast, is a temporary measure that opens the door to a cascade of secondary interventions, each with its own risks. The two procedures embody opposing strategies in neurosurgery: one seeks precision; the other, survival at any cost. Yet the reality is rarely so binary. Many patients fall into a middle ground where neither option is ideal, forcing surgeons to improvise. The most revealing insight is how craniotomy vs craniectomy exposes the limits of modern medicine. Even with advanced technology, neurosurgery remains a high-stakes gamble. The choice isn’t just about the patient’s anatomy—it’s about their values, their family’s expectations, and the resources available to them. As healthcare systems grapple with rising costs and aging populations, these decisions will only grow more complex. The goal, then, isn’t to declare one procedure superior but to ensure that every patient—and their loved ones—understands the full spectrum of possibilities before the scalpel is lifted.| Factor | Craniotomy | Craniectomy |
|---|---|---|
| Primary Goal | Access for resection, biopsy, or repair (e.g., tumor removal, aneurysm clipping) | Emergency decompression to relieve intracranial pressure |
| Skull Flap | Removed temporarily, replaced and secured with plates | Removed permanently; requires later cranioplasty |
| Typical Context | Elective surgery for planned procedures | Emergency surgery for trauma, stroke, or malignant edema |
| Long-Term Risks | Seizures, cognitive deficits, infection at surgical site | Chronic subdural hematomas, hydrocephalus, "sinking skin flap" syndrome |

Conclusion
The debate over craniotomy vs craniectomy is more than a technical discussion—it’s a window into the fragility of the human brain and the ethical dilemmas of modern medicine. What separates these procedures isn’t just the hardware but the assumptions they carry: one assumes the brain can be treated without immediate decompression; the other assumes it cannot. The reality is that neither assumption is always correct, which is why these decisions are among the most difficult in neurosurgery. For patients and families, the lack of clarity can be devastating. Surgeons are trained to act swiftly, but the consequences of those actions can ripple for years. As research progresses, the hope is that craniotomy vs craniectomy will become less about choosing between two imperfect options and more about tailoring interventions to individual patients. Until then, the conversation must remain open—because the stakes are nothing less than the quality of a life saved.Comprehensive FAQs
Q: What’s the most common reason a patient would need a craniectomy instead of a craniotomy?
A: The primary indication for a craniectomy is elevated intracranial pressure (ICP) that cannot be controlled with medical management alone. This typically occurs in cases of traumatic brain injury with diffuse swelling, massive intracranial hemorrhage, or malignant cerebral edema (e.g., from a large stroke or tumor). If the brain is herniating or ICP exceeds 25 mmHg despite maximal medical therapy, a craniectomy is often the only way to prevent immediate death. Craniotomies, by contrast, are used when the goal is controlled access for procedures like tumor resection or aneurysm clipping, where the brain’s swelling is manageable.
Q: Can a craniectomy patient ever regain full neurological function?
A: While rare, some patients who undergo decompressive craniectomy do achieve near-full recovery, particularly if the procedure is performed early and the underlying cause (e.g., a clot or hemorrhage) is addressed. However, studies suggest that only about 20–40% of survivors return to independent living with minimal deficits. The majority face permanent impairments, such as hemiparesis, aphasia, or cognitive deficits. The likelihood of recovery depends on factors like the patient’s age, the duration of elevated ICP before surgery, and whether secondary complications (e.g., infections or hydrocephalus) arise post-operatively.
Q: How soon after a craniectomy is a cranioplasty typically performed?
A: The timing of cranioplasty—the procedure to replace the missing skull flap—varies widely but is generally delayed until the brain has stabilized and the patient can tolerate another surgery. Most centers aim for 3 to 6 months post-craniectomy, though some wait up to two years, especially in elderly or frail patients. The delay is necessary because the brain may still be swollen or vulnerable to infection. However, prolonged exposure increases the risk of complications like subdural hematomas or "sinking skin flap" syndrome, where the brain shifts downward, worsening neurological function.
Q: Are there any non-surgical alternatives to a craniectomy for relieving ICP?
A: Yes, several non-surgical or minimally invasive options can be attempted before resorting to a craniectomy. These include:
- Medical management: Osmotic agents (mannitol, hypertonic saline), diuretics, or barbiturate-induced coma to reduce cerebral edema.
- External ventricular drainage (EVD): Placing a drain to lower cerebrospinal fluid (CSF) pressure.
- Decompressive craniectomy via burr holes: Some centers use smaller openings to relieve pressure without full craniectomy, though this is less common.
- Hypothermia therapy: Cooling the brain to reduce metabolic demand and swelling.
Q: What are the biggest misconceptions about craniotomies and craniectomies?
A: Three persistent myths distort the public understanding of craniotomy vs craniectomy:
- "A craniotomy is always safer than a craniectomy." While craniotomies carry lower immediate mortality risks, they’re not always the better choice. In cases of severe swelling, a craniotomy could worsen herniation by restricting the brain’s ability to expand.
- "Craniectomy patients will always be left with severe disabilities." While many do face long-term deficits, a subset achieves remarkable recoveries—especially children and younger adults with reversible causes of ICP elevation.
- "The skull flap is always reattached in a craniotomy." In some cases, surgeons may leave the flap off temporarily (a "delayed cranioplasty") if the brain remains swollen post-surgery.
Q: How do insurance companies and hospitals typically cover the costs of craniectomy and cranioplasty?
A: Coverage varies by country and insurer, but in the U.S., craniectomy and cranioplasty are generally considered medically necessary when performed for life-threatening conditions. However, challenges arise in cases where:
- The patient’s prognosis is deemed poor (some insurers may deny coverage for cranioplasty if the patient is unlikely to benefit).
- There are delays in scheduling cranioplasty due to resource constraints (patients may face pressure to "wait their turn" in overburdened systems).
- The patient requires long-term rehabilitation, which insurers may limit in scope or duration.
Q: Are there any emerging technologies that could reduce the need for craniectomies?
A: Research is focused on three key areas to minimize the need for decompressive craniectomy:
- Predictive biomarkers: Blood tests or imaging that can identify patients at high risk of malignant cerebral edema before it becomes irreversible.
- Advanced ICP monitoring: Wearable or implantable devices that provide real-time pressure data, allowing earlier intervention with medical therapies.
- Neuroprotective drugs: Experimental compounds (e.g., certain anti-inflammatory or anti-apoptotic agents) that could reduce brain swelling at the cellular level.
