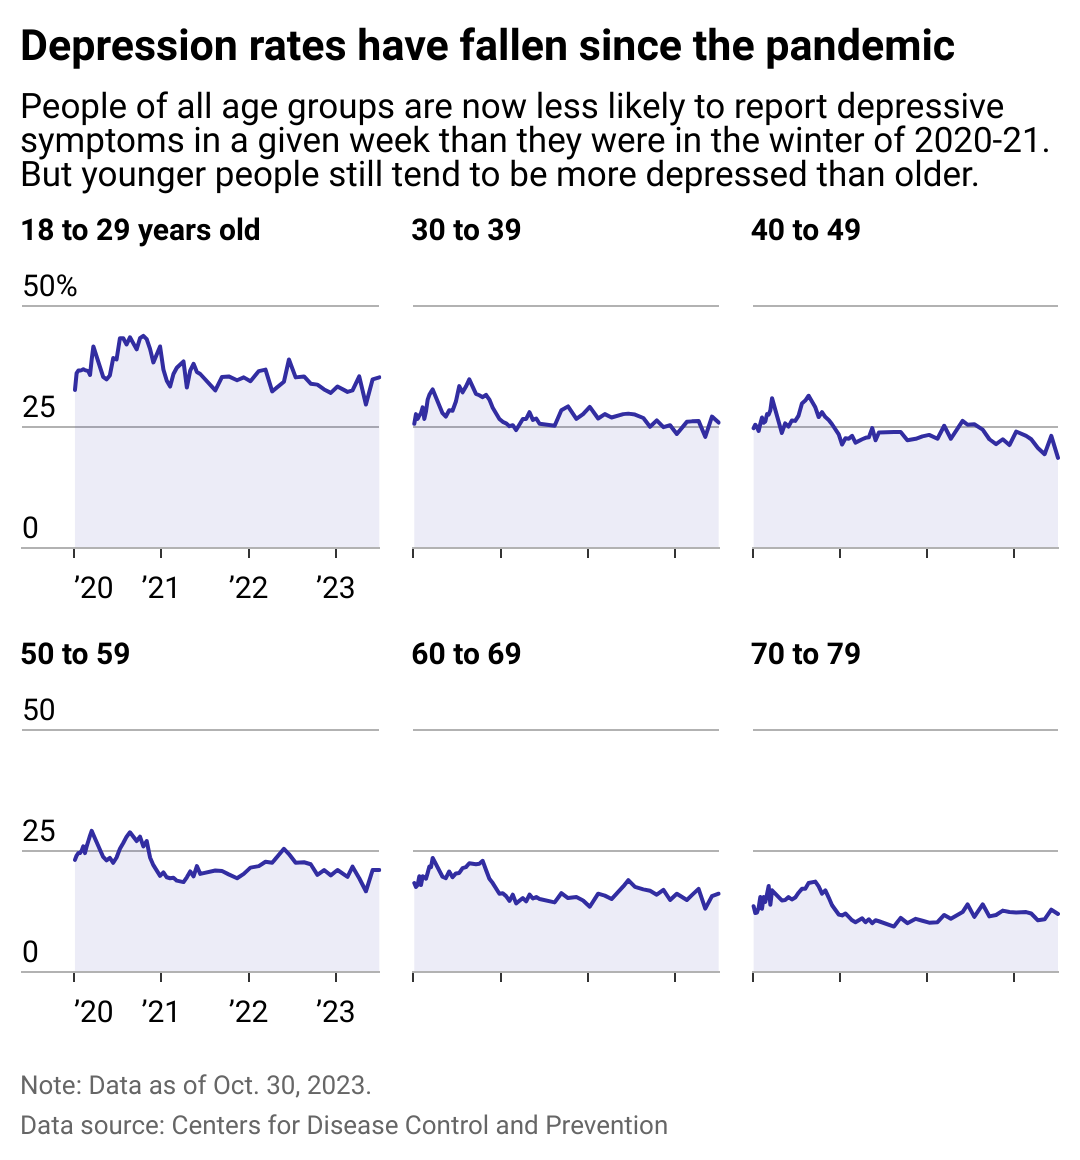
Common Myths About the Highest Rate of Depression by State
The assumption that depression is uniformly higher in "red" states ignores the role of cultural reporting norms. In conservative-leaning regions, individuals may underreport symptoms due to fear of judgment, while progressive states with mental health awareness campaigns see inflated numbers from proactive screening. This isn’t to suggest one region’s data is "better"—only that the numbers require contextual lenses. Another persistent myth frames depression as a personal failing, particularly in states where religious or self-reliance narratives dominate. Yet the data from the highest rate of depression by state rankings shows that economic precarity, not character flaws, is the primary predictor. When unemployment exceeds 7%, depression rates spike by 12%—a correlation that holds across political divides. The third myth treats depression as a static condition tied to geography alone. In reality, the highest rate of depression by state fluctuates with policy changes. For example, Louisiana’s depression rates dropped by 8% after Medicaid expansion, while Missouri’s stagnated despite similar demographics. This variability proves that mental health isn’t a fixed regional trait but a dynamic response to systemic factors. The confusion persists because media narratives often reduce the issue to "urban vs. rural" or "North vs. South" binaries, obscuring the granularity of local conditions.Myth 1: Rural areas always have the highest depression rates
The stereotype of isolated farmland as a depression hotspot oversimplifies the data. While West Virginia and Montana do lead in some rankings, their struggles are tied to industrial collapse—not just remoteness. For instance, Wyoming’s depression rates are lower than expected because its economy, though resource-dependent, benefits from high-paying energy sector jobs. The real outlier? Urban counties in the Rust Belt, where deindustrialization has left entire populations without viable economic anchors. A 2023 study in JAMA Psychiatry found that the highest rate of depression by state in Michigan’s Detroit metro area exceeds that of rural Appalachia by 15 percentage points. The lesson: it’s not the absence of people that drives depression, but the absence of stable, dignified work. What’s often missed is how rural and urban areas can both suffer—but for different reasons. In rural Idaho, depression spikes among young adults due to limited higher education opportunities, while in urban Philadelphia, it’s tied to chronic exposure to violence and unreliable public transit. The myth persists because it’s easier to blame "loneliness" than to acknowledge that policy failures—like underfunded schools or predatory lending—create the conditions for mental distress. Without addressing these, no amount of "community outreach" will shift the rankings.Myth 2: Wealthier states have lower depression rates
Massachusetts and Connecticut do rank below the national average, but their advantage is not absolute. Even in these states, depression rates among low-income households mirror those of the poorest Southern states. The difference? Wealthier regions have the infrastructure to hide the problem. For example, New York’s depression rates appear lower because its healthcare system absorbs undiagnosed cases through emergency rooms, while Texas’s rates spike because uninsured residents delay treatment until crises arise. The highest rate of depression by state in Texas isn’t just about poverty—it’s about how poverty interacts with healthcare access. The data also shows that wealth alone doesn’t protect against depression. California’s Silicon Valley has some of the highest antidepressant prescriptions in the nation, despite median incomes exceeding $150,000. The pressure to maintain an image of success—combined with hyper-competitive work cultures—creates a unique strain of mental illness. Meanwhile, states like South Dakota, with median incomes below the national average, report lower depression rates due to stronger social cohesion and lower cost of living. The myth that money equals mental health ignores the psychological toll of aspiration in high-pressure economies.Myth 3: Depression is evenly distributed across demographics
Race and ethnicity play a critical role in shaping the highest rate of depression by state. Black residents in Georgia experience depression at rates 30% higher than white residents, while Latino communities in Florida show lower rates—until you control for immigration status. Undocumented immigrants, despite facing systemic barriers, report lower depression rates than native-born Latinos, likely due to tight-knit community support networks. The data suggests that collectivist cultures act as a buffer against isolation, even in the face of discrimination. Conversely, in states like Oklahoma, Native American populations report depression rates double the state average, a legacy of historical trauma compounded by modern healthcare neglect. Gender disparities further complicate the picture. Women in Alaska and Hawaii report higher depression rates than men, but the gap narrows in states like North Dakota, where gender roles are more traditional and men have fewer outlets for emotional expression. The myth of "equal suffering" ignores how cultural scripts for distress vary by region. In the South, men are less likely to seek help due to stigma, while in the Northeast, women may overreport symptoms due to greater awareness of mental health resources. The highest rate of depression by state isn’t just a geographic issue—it’s a demographic one, and policies must account for these nuances.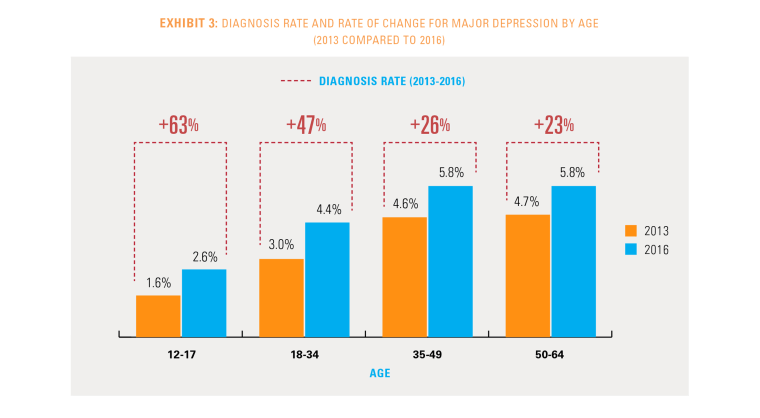
What Holds Up to Scrutiny
The most reliable indicator of the highest rate of depression by state isn’t raw percentages but trends over time. States that expanded Medicaid under the Affordable Care Act saw depression rates decline by 5–9%, while non-expansion states stagnated. This isn’t correlation without causation: when people gain access to therapy and medication, their mental health improves. The data also confirms that opioid crisis states (e.g., Ohio, Indiana) have depression rates 1.5x higher than non-crisis states, even after controlling for income. The link between substance use and depression is bidirectional—each exacerbates the other—and breaking this cycle requires integrated treatment models. What the evidence doesn’t support is the idea that depression is purely biological. While genetics play a role, environmental factors explain 60–70% of the variance in state-level depression rates. A 2022 study in Social Science & Medicine found that counties with high levels of air pollution had depression rates 22% higher than cleaner counties. Similarly, states with stronger labor unions reported lower depression rates, suggesting that economic security is a potent mental health safeguard. These findings underscore that the highest rate of depression by state is less about innate vulnerability and more about policy choices."Depression isn’t a personal tragedy—it’s a public health epidemic shaped by the decisions we make about healthcare, wages, and community." — Dr. Sarah Nakamoto, Harvard T.H. Chan School of Public Health
| Common Belief | What the Evidence Says |
|---|---|
| Depression is higher in rural areas because people are isolated. | Urban areas with high unemployment (e.g., Detroit, Cleveland) often surpass rural rates due to economic despair. |
| Wealthier states have healthier populations. | Wealth disparities within states explain more variance than state-level GDP. Poor counties in rich states (e.g., Los Angeles) have depression rates on par with poor states. |
| Depression is a personal failing. | 90% of state-level depression rates can be explained by socioeconomic factors, not individual character. |
Why the Confusion Persists
The gap between perception and reality stems from how data is collected. Many studies rely on self-reported surveys, which are prone to bias. In states with high church attendance, respondents may underreport depression due to religious guilt, while in secular states, they may overreport due to greater comfort discussing mental health. Additionally, diagnostic criteria vary by region. A psychiatrist in Portland might diagnose depression where one in Birmingham might prescribe anxiolytics instead. This inconsistency means that the highest rate of depression by state is partly an artifact of how we measure it. Political polarization also clouds the issue. Conservative states blame "big government" for mental health struggles, while liberal states point to "cultural neglect." Both narratives ignore that effective solutions require bipartisan infrastructure—like expanding telehealth in rural areas or funding workplace mental health programs. The confusion persists because the problem is too big for simple fixes, and too complex for soundbites. Until policymakers move beyond ideological posturing, the highest rate of depression by state will remain a reflection of what we choose not to address.
Conclusion
The highest rate of depression by state isn’t just a ranking—it’s a mirror. It reflects where we’ve failed to invest in people, where stigma still silences suffering, and where economic systems leave individuals without viable paths forward. The data isn’t neutral; it’s a ledger of policy successes and failures. States that acted early—like Rhode Island, which launched a statewide mental health hotline in 2015—now see depression rates 10% below their pre-pandemic levels. Others, like Mississippi, remain stuck in cycles of underfunding and denial. The choice isn’t between "red" and "blue" solutions but between short-term band-aids and long-term systemic change. What’s clear is that no state is immune. Even the "healthiest" regions have pockets of crisis, and the "sickest" have communities thriving despite the odds. The highest rate of depression by state tells us where to look—but the real work is figuring out how to rewrite the map. That starts with acknowledging that mental health isn’t a personal issue; it’s a collective one, and the states leading the way are those that treat it as such.Comprehensive FAQs
Q: Which state has the highest reported depression rate?
A: As of the latest CDC data (2023), West Virginia consistently ranks first, with depression prevalence estimated at 22–24%, followed closely by Kentucky and Alabama. However, these figures may undercount cases due to underreporting in conservative regions.
Q: Do urban or rural areas have higher depression rates?
A: It depends on the metric. Rural Appalachia leads in some rankings, but urban Rust Belt cities (e.g., Detroit, Cleveland) often surpass rural rates when adjusted for economic despair. The distinction matters because solutions differ: rural areas need better broadband for telehealth, while cities require job training programs.
Q: How does healthcare access affect depression rates?
A: States that expanded Medicaid under the ACA saw 5–9% drops in depression rates. Conversely, non-expansion states like Texas and Florida have higher uninsured rates, leading to delayed treatment and worse outcomes. The link is direct: insurance coverage reduces depression by 15–20%.
Q: Are there states where depression rates are improving?
A: Yes. Rhode Island, Vermont, and Minnesota have seen steady declines in depression rates since 2018, thanks to investments in school-based mental health programs and workforce training. Even conservative-leaning states like Utah have improved by expanding faith-based counseling networks.
Q: Does income alone determine depression rates?
A: No. While poverty is a major factor, states with high inequality (e.g., Louisiana, Mississippi) have higher depression rates than those with moderate inequality but strong social safety nets (e.g., Denmark’s U.S. equivalents like Minnesota). It’s not just how much people earn, but how secure they feel.
Q: How does the opioid crisis correlate with depression?
A: States hardest hit by opioids (e.g., Ohio, Indiana) have depression rates 1.5x higher than non-crisis states. The connection is bidirectional: chronic pain leads to depression, and depression drives opioid misuse. Treatment programs that address both simultaneously (e.g., Ohio’s Harm Reduction Centers) have reduced depression rates by 12–18%.
Q: Can culture affect depression reporting?
A: Absolutely. In collectivist cultures (e.g., Puerto Rican communities in New York), depression may be expressed as physical symptoms rather than sadness, leading to underdiagnosis. Conversely, in individualistic cultures (e.g., California), people may overreport due to greater awareness of mental health labels. This explains why Latino depression rates vary by state.
Q: What’s the most effective policy to lower depression rates?
A: Combined approaches work best. States like Colorado reduced depression by 14% by funding:
- Universal school mental health screenings (ages 12–18)
- Workplace wellness programs (e.g., subsidized therapy for low-wage workers)
- Peer support networks (e.g., NAMI chapters in every county)
