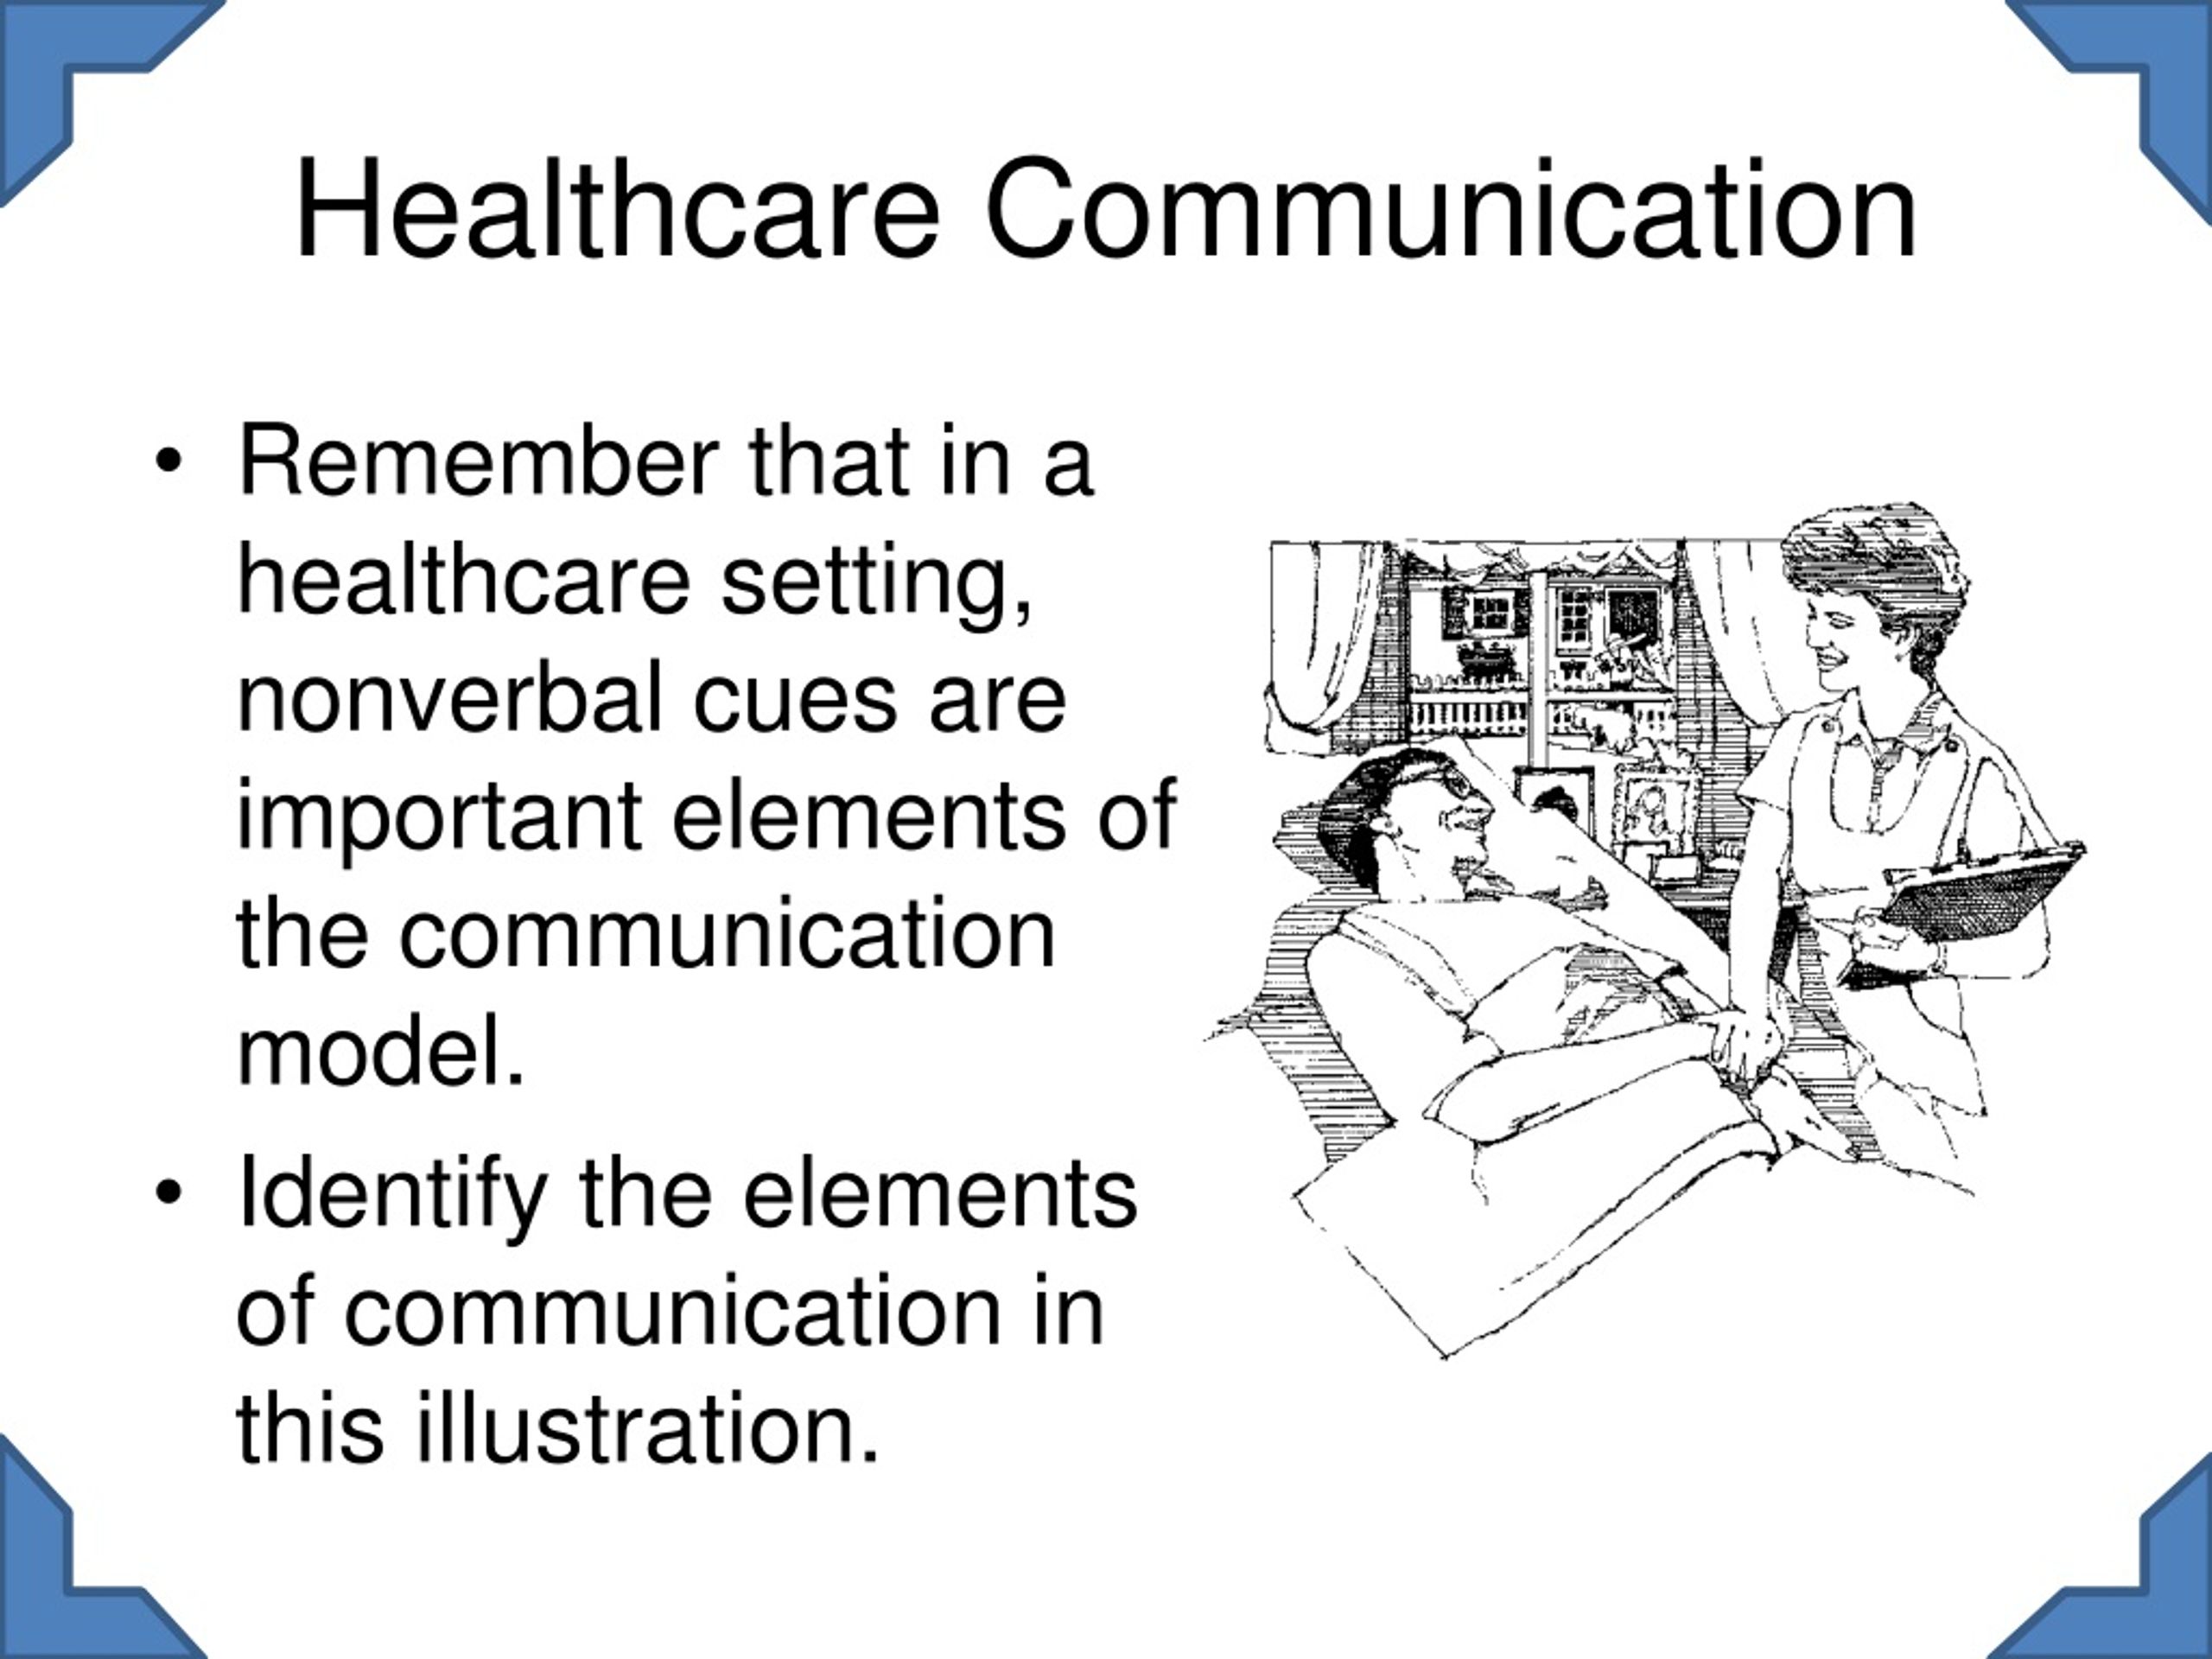
The Complete Overview of Communication in Healthcare
Communication in healthcare is the invisible architecture of the medical system—supporting everything from routine check-ups to critical care decisions. At its core, it encompasses verbal exchanges, written records, nonverbal cues, and even the design of hospital environments. The goal isn’t just to inform but to align—ensuring that patients, families, and providers share the same understanding of risks, benefits, and next steps. This alignment is fragile; a single misinterpreted instruction can derail months of treatment. For example, a 2021 study in The BMJ found that 30% of medication errors stemmed from communication failures, whether in handoffs between shifts or in patient instructions. The field has evolved beyond the traditional doctor-patient dyad. Today, healthcare communication spans interdisciplinary teams, digital platforms, and even artificial intelligence tools that parse patient sentiment. Telemedicine, for instance, has forced providers to master new forms of nonverbal communication—through screen-sharing, virtual waiting rooms, and the subtle art of reading facial expressions in pixelated video calls. Meanwhile, electronic health records (EHRs) have introduced new risks: providers now spend nearly two hours per day documenting in systems that prioritize data entry over human connection. The paradox is stark: technology was supposed to streamline care, yet it often complicates the very communication it aims to improve.Historical Background and Evolution
The roots of modern healthcare communication trace back to the 19th century, when the rise of scientific medicine created a divide between laypeople and medical experts. Before then, healers relied on oral traditions, herbal knowledge, and community trust—communication was collaborative, not hierarchical. The shift toward specialized language and institutional authority began with the Flexner Report of 1910, which standardized medical education and distanced practitioners from public understanding. By the mid-20th century, the paternalistic model dominated: doctors made decisions, patients complied. This approach ignored patient autonomy until the 1970s, when bioethics movements pushed for shared decision-making. The 1990s marked a turning point with the rise of patient-centered care, influenced by studies showing that clear communication improved outcomes. The Institute of Medicine’s 1999 report To Err Is Human highlighted communication breakdowns as a leading cause of medical errors, prompting hospitals to adopt protocols like SBAR (Situation-Background-Assessment-Recommendation) for structured handoffs. Today, healthcare communication is governed by frameworks like the Swiss Cheese Model (James Reason), which treats miscommunication as a series of overlapping failures—each slice of cheese represents a barrier (e.g., protocols, training, culture) that must align to prevent errors. Yet despite these advancements, disparities persist. Marginalized communities often face language barriers, cultural misunderstandings, or outright dismissal of their symptoms—a legacy of systemic inequities in medical training.Core Mechanisms: How It Works
The mechanics of effective healthcare communication hinge on three pillars: clarity, empathy, and systems integration. Clarity begins with plain language—avoiding jargon like "noncompliant" (which implies blame) in favor of "needs support." Empathy involves active listening: studies show that interrupting a patient after 18 seconds reduces their satisfaction and comprehension. Systems integration, meanwhile, demands seamless handoffs. For instance, the I-PASS protocol, used in pediatric hospitals, structures verbal handoffs to include Illness severity, Patient summary, Action list, Situation awareness, and Synthesis. When implemented, it reduces adverse events by 30%. Yet the human element remains the wild card. A 2022 study in JAMA Network Open found that 68% of patients felt their doctors didn’t listen well, and 40% reported being rushed. The pressure to see more patients per hour creates a feedback loop: providers cut corners on explanation, patients feel dismissed, and trust erodes. Digital tools like health literacy apps or AI-powered translators aim to fill gaps, but they’re no substitute for the nuanced judgment of a skilled communicator. For example, a pharmacist might explain a drug’s side effects in technical terms to a medical student but must simplify for an elderly patient with low literacy. The challenge lies in adapting without losing precision.Key Benefits and Crucial Impact
The impact of strong healthcare communication is measurable across outcomes, costs, and patient satisfaction. A 2023 meta-analysis in The Lancet found that patient-centered communication reduced hospital readmissions by 22% and improved medication adherence by 35%. The financial stakes are clear: every dollar invested in communication training can save $2 to $5 in avoided complications. Yet the benefits extend beyond metrics. A well-delivered diagnosis can ease a family’s grief; a clear post-op instruction can prevent a fall. Conversely, poor communication fuels medical mistrust, particularly among minority groups, where historical abuses (e.g., the Tuskegee syphilis study) cast a long shadow. The emotional toll is often overlooked. A 2021 survey by the Journal of General Internal Medicine revealed that 73% of patients who felt their concerns were dismissed during a visit reported higher anxiety levels. For providers, the strain is equally real: burnout rates exceed 50% in some specialties, partly due to the emotional labor of breaking bad news or managing family conflicts. The system’s failure to prioritize human connection isn’t just inefficient—it’s ethically problematic. As the late oncologist Atul Gawande noted, "Good medicine is as much about listening as it is about curing.""Communication is the bridge between healing and harm. Without it, even the most skilled hands are useless." — Dr. Abraham Verghese, Stanford University
Major Advantages
- Reduced errors: Structured communication protocols (e.g., SBAR, I-PASS) cut miscommunication-related errors by 20–40%.
- Higher adherence: Patients who understand their treatment plans are 3x more likely to follow through, reducing wasted spending on unused prescriptions.
- Lower litigation risk: Clear documentation and patient consent processes decrease malpractice claims by 15–25%, according to hospital risk management data.
- Improved mental health: Empathetic communication lowers patient anxiety by 40%, particularly in chronic illness management.

Comparative Analysis
| Traditional Communication | Modern/Digital Communication |
|---|---|
| Face-to-face, high-trust, but time-consuming. Relies on nonverbal cues. | Faster, scalable (e.g., telehealth), but risks depersonalization. Requires tech literacy. |
| Prone to bias (e.g., gender, racial stereotypes in diagnoses). | Can mitigate bias with structured tools (e.g., AI audit trails), but may introduce new biases in algorithms. |
| Documentation is manual, error-prone (e.g., illegible handwriting). | EHRs standardize records but create alert fatigue (providers ignore critical warnings). |
Future Trends and Innovations
The next decade of healthcare communication will be shaped by AI and predictive analytics, though with caution. Tools like IBM Watson Health already analyze patient conversations to flag depression or non-adherence, but their accuracy hinges on high-quality training data—a challenge given global healthcare disparities. Meanwhile, virtual reality (VR) simulations are being tested to train providers in break-the-bad-news scenarios, offering a safer space to practice empathy. However, these innovations risk dehumanizing care if not balanced with human judgment. Culturally, the push for patient autonomy will demand new skills. Gen Z patients, accustomed to instant gratification and transparency, expect real-time access to their records and collaborative decision-making. Hospitals are responding with patient portals and shared decision aids, but adoption remains uneven. The biggest wild card? Regulation. As AI tools enter clinical workflows, questions about accountability (e.g., who’s liable if an AI misinterprets a patient’s tone?) will force a reckoning with ethical communication frameworks. One thing is certain: the future will belong to systems that prioritize both technology and humanity.
Conclusion
Communication in healthcare is the invisible thread holding together a complex, high-stakes ecosystem. It’s where science meets storytelling, where data intersects with emotion, and where small words—like "soon," "likely," or "side effects"—can carry life-altering weight. The system’s flaws are well-documented, but so are its triumphs: the surgeon who pauses to ask, "What are your fears?"; the nurse who translates not just language but also fear; the primary care doctor who spends 10 minutes explaining a test result. These moments don’t just improve outcomes—they restore dignity to the process of healing. The path forward isn’t about replacing human connection with algorithms but about augmenting it. That means investing in communication training as rigorously as surgical skills, designing healthcare environments that reduce noise and stress, and holding providers accountable for both competence and compassion. The alternative—a system where efficiency outweighs empathy—is one where patients become numbers, and trust becomes a liability. The choice isn’t between speed and care; it’s between two forms of speed: the hurried rush that leads to errors, and the deliberate pace that saves lives.Comprehensive FAQs
Q: How can patients improve communication with their doctors?
A: Prepare a list of questions or symptoms beforehand, bring a trusted advocate (family member or friend), and don’t hesitate to ask for clarification—even if it means saying, "I didn’t understand that. Can you explain it differently?" Studies show that patients who take notes during visits retain more information and feel more involved in their care.
Q: What’s the best way for hospitals to reduce communication errors?
A: Implement structured handoff protocols (e.g., SBAR or I-PASS), standardize medication labeling (e.g., tall-man lettering for look-alike drugs), and invest in interdisciplinary training where nurses, doctors, and pharmacists practice simulated crises. Technology like smart IV pumps that flag dosage errors can also help, but human oversight remains critical.
Q: Are there cultural differences in healthcare communication?
A: Absolutely. In collectivist cultures (e.g., many Asian or Latin American communities), patients may defer to family decisions, while in individualist cultures (e.g., U.S. or Western Europe), autonomy is prioritized. High-context cultures (e.g., Japan) rely on nonverbal cues, while low-context cultures (e.g., Germany) expect explicit instructions. Providers must adapt their approach—for example, using visual aids for patients from oral traditions or interpreters who understand medical jargon, not just language.
Q: How does telemedicine affect doctor-patient communication?
A: Telemedicine compresses nonverbal cues (e.g., eye contact, body language) and can make it harder to gauge a patient’s emotional state. However, it also democratizes access for rural or disabled patients. Best practices include longer virtual visits to compensate for lost cues, clearer screen instructions (e.g., "Look at the camera, not the screen"), and follow-up calls to check understanding. Some clinics now use AI sentiment analysis to flag distress in a patient’s voice, though privacy concerns remain.
Q: What role does humor play in healthcare communication?
A: Humor can reduce stress, improve rapport, and even aid memory—if used appropriately. A well-timed joke can ease tension during a difficult diagnosis, but it must be patient-centered (e.g., not making light of their condition). Research in Patient Education and Counseling shows that lighthearted interactions increase patient satisfaction, but providers must gauge the patient’s comfort level—what’s funny to one may feel dismissive to another. Dark humor, sarcasm, or jokes about weight/appearance should always be avoided.
