6 Things Worth Knowing About What Medical Profession Has the Highest Suicide Rate
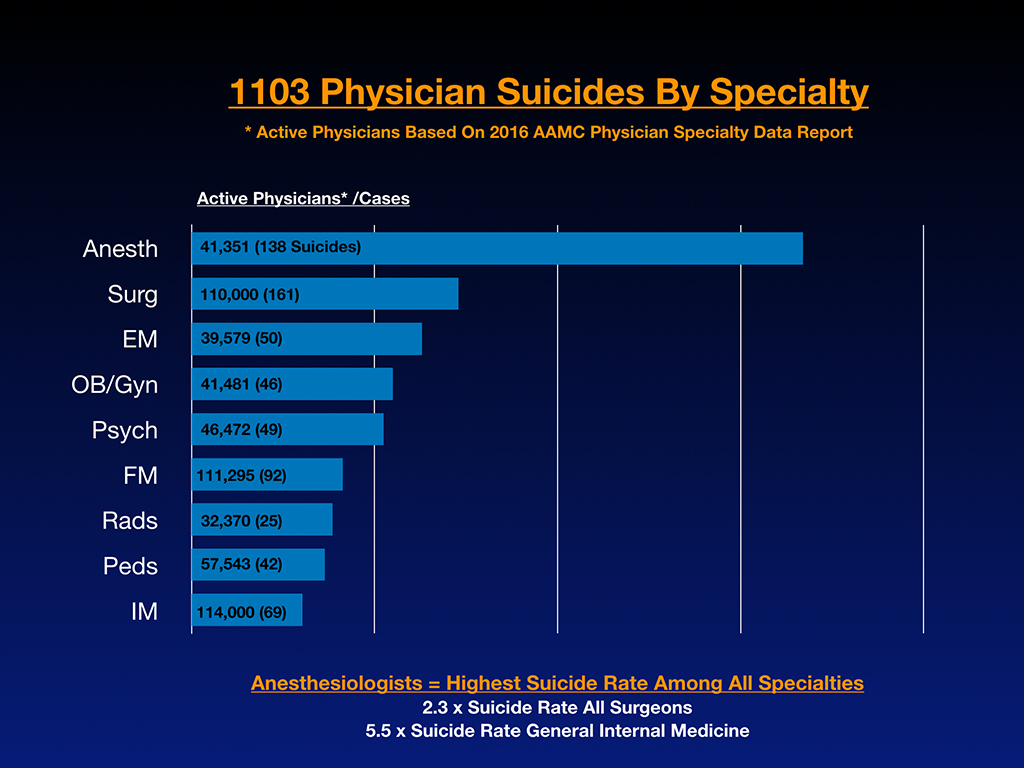
The conversation about suicide in medicine often centers on psychiatrists, but the reality is more nuanced. While psychiatrists do face disproportionate risks, other specialties—particularly those involving direct patient trauma or extreme workloads—demonstrate similarly alarming patterns. The six facts below expose the breadth of the problem, the specific vulnerabilities of certain professions, and the systemic failures that perpetuate the cycle.1. Psychiatrists Top the List—but Not by Much
Psychiatrists have long been identified as the medical profession with the highest suicide rate, with studies consistently placing them at the forefront. The reasons are multifaceted: they confront the darkest aspects of human psychology daily, grapple with ethical dilemmas around patient autonomy and treatment limits, and often carry the emotional burden of failed interventions. A 2019 study in JAMA Psychiatry found that psychiatrists die by suicide at a rate 40% higher than other physicians—a figure that, while shocking, may still underrepresent the true scale, given underreporting in medical death certificates. Yet the gap between psychiatrists and other high-risk specialties is narrower than assumed. Emergency medicine physicians, for instance, operate in high-pressure environments where moral distress—watching patients die despite their best efforts—is chronic. The American Foundation for Suicide Prevention notes that EM doctors report burnout rates exceeding 70%, a direct correlate to suicide risk. The key difference? Psychiatrists are more likely to be diagnosed with depression or anxiety before their deaths, while EM physicians may mask their struggles behind the adrenaline of the job.2. Obstetricians and Gynecologists Face a Silent Crisis
The field of obstetrics and gynecology (OB-GYN) is another where the suicide rate among practitioners rivals that of psychiatrists. A 2020 Obstetrics & Gynecology study revealed that OB-GYNs die by suicide at rates nearly double those of the general population. The reasons are tied to the emotional toll of delivering babies while managing high-risk pregnancies, the pressure to maintain perfection in a field where mistakes can be fatal, and the isolation of rural practice. Many OB-GYNs work in underserved areas with limited peer support, compounding the stress. What’s particularly troubling is the gender disparity in how these risks manifest. Female OB-GYNs, who make up the majority of the specialty, report higher rates of depression and suicidal ideation than their male counterparts—yet they are less likely to seek treatment due to stigma and the expectation to "handle it." The suicide rate in this group is a stark reminder that what medical profession has the highest suicide rate isn’t always the one with the most publicized crisis; sometimes, it’s the one where systemic neglect goes unnoticed.3. Emergency Medicine: The Adrenaline Masking Depression
Emergency medicine is a profession built on crisis management, where physicians thrive on the rush of high-stakes interventions. This culture of resilience can obscure the fact that EM doctors are among the most suicide-prone in medicine. A 2021 study in Annals of Emergency Medicine found that EM physicians die by suicide at rates comparable to psychiatrists, though the causes differ. Where psychiatrists grapple with existential weight, EM doctors face moral injury—the psychological harm from witnessing preventable deaths, ethical conflicts, and the inability to provide adequate care due to systemic constraints. The problem is exacerbated by the shift-work nature of EM, which disrupts circadian rhythms and social support networks. Many EM physicians develop coping mechanisms—substance use, perfectionism, or emotional detachment—that, over time, erode mental health. The irony? The same traits that make them excel in emergencies—stoicism, problem-solving under pressure—can become liabilities when untreated.4. Dentists: The Overlooked Frontline Workers
Dentistry is rarely discussed in the context of suicide rates, yet it ranks among the top professions for physician suicides. A 2018 Journal of the American Dental Association analysis found that dentists die by suicide at a rate 40% higher than the general population—higher even than physicians in some specialties. The reasons are rooted in the financial pressures of private practice, the physical toll of repetitive motions leading to chronic pain, and the social isolation of solo practitioners. Many dentists operate in financially precarious environments, with student debt and malpractice fears creating a perfect storm for despair. What makes dentistry unique is the lack of institutional safety nets. Unlike hospital-based physicians, dentists often work alone, with limited access to mental health resources. The stigma around seeking help in dentistry is particularly strong, as the profession has historically prioritized resilience over vulnerability. This silence contributes to the high suicide rate—a silent epidemic within an already overlooked field.5. The Role of Medical Training in Suicide Risk
The pipeline into medicine itself may contribute to the elevated suicide rates in certain specialties. Medical training is notoriously grueling, with residents reporting depression rates as high as 60% during their early years. Specialties that require the longest training—such as psychiatry, neurology, and surgery—often see higher burnout and suicide rates among their practitioners. The culture of "toughing it out" during residency, combined with sleep deprivation and high-stakes evaluations, sets the stage for long-term mental health struggles. A 2022 Mayo Clinic Proceedings study highlighted that physicians who enter specialties with high emotional labor—fields where they must constantly manage patient distress—are at greater risk. Psychiatrists and OB-GYNs fit this profile, but so do primary care physicians, who often bear the brunt of unmet patient needs without adequate support. The training environment doesn’t just shape clinical skills; it shapes how physicians cope with failure—and whether they’re equipped to ask for help."Medical schools teach us how to save lives, but they don’t teach us how to save ourselves. That’s the gap we’re failing to address." — Dr. Pamela Wible, physician and suicide prevention advocate
6. Systemic Failures: Why the Crisis Persists
The most glaring truth about which medical profession has the highest suicide rate is that the answer changes depending on how you measure it. Psychiatrists lead in some studies, EM physicians in others, and dentists in yet another. The common denominator? A healthcare system that prioritizes productivity over well-being, and a culture that penalizes vulnerability. Physicians are trained to diagnose and treat others but are often denied the same care when they need it. Insurance barriers, the lack of mental health parity in medical licensing, and the fear of career repercussions for seeking help all contribute to the silence. The data also reveals a generational divide. Younger physicians, particularly those entering the field post-2010, report higher rates of depression and suicidal ideation than their predecessors. This cohort entered medicine during the height of the opioid crisis, the COVID-19 pandemic, and a time when medical debt was reaching unprecedented levels. The combination of these factors has created a perfect storm for mental health collapse.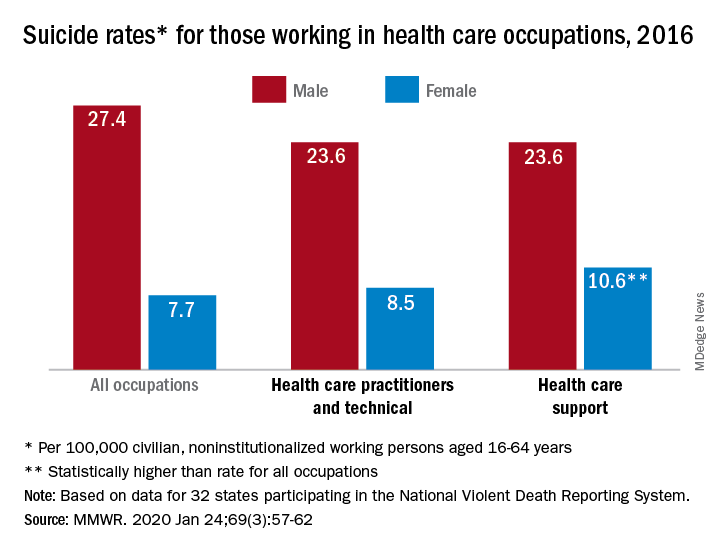
How These Facts Connect
The six facts above paint a portrait of a crisis that is both specialized and systemic. While psychiatrists and OB-GYNs often top lists of what medical profession has the highest suicide rate, the underlying causes are shared across specialties: isolation, moral distress, financial strain, and a lack of institutional support. The emergency medicine physician who dies by suicide after years of untreated burnout shares structural risks with the dentist drowning in debt, even if their daily experiences differ. The training pipeline, the culture of stoicism, and the absence of mental health resources in medical workplaces create a feedback loop that traps practitioners in silence. What’s most alarming is how these risks are amplified by external factors. The COVID-19 pandemic, for example, saw suicide rates among healthcare workers spike by 30% in some studies, with frontline physicians—particularly those in high-stress specialties—bearing the brunt. The pandemic laid bare what had long been hidden: that the medical profession’s suicide crisis is not an isolated issue but a symptom of a larger failure in how society values care workers. The table below compares the three most affected groups and their key risk factors:| Specialty | Primary Risk Factors | Unique Challenges |
|---|---|---|
| Psychiatry | Emotional labor, moral injury, high patient distress | Stigma around seeking help, diagnostic bias (physicians may not recognize their own depression) |
| Obstetrics/Gynecology | High-stakes decision-making, isolation in rural practice, gendered stigma | Financial pressures of private practice, lack of peer support networks |
| Emergency Medicine | Moral injury, shift work, adrenaline masking depression | Culture of resilience, limited mental health resources in ED settings |

Conclusion
The question of which medical profession has the highest suicide rate is not just a statistical exercise—it’s a mirror held up to the failures of modern medicine. Psychiatrists, OB-GYNs, EM physicians, and dentists all reflect the same broken system: one that asks its workers to perform miracles while offering little in return. The data is clear, but the will to act remains lacking. Mental health resources in medical schools are still treated as an afterthought, peer support programs are underfunded, and the stigma around seeking help persists despite decades of awareness campaigns. The good news? Change is possible. Programs like the Physician Well-Being Initiative and The Doctors Company’s peer support networks have shown that structured intervention can reduce suicide risk by up to 50% in high-risk specialties. The challenge is scaling these efforts across all medical fields—particularly those where the crisis is least visible. Dentists, for instance, have begun forming collective mental health funds, while EM residency programs are integrating mandatory wellness check-ins. These are steps in the right direction, but they must become standard practice, not exceptions. The medical community has a choice: continue treating suicide as an individual tragedy or recognize it as a systemic epidemic that demands collective action. The answer to what medical profession has the highest suicide rate is no longer enough. The question now is whether the system will finally listen.Comprehensive FAQs
Q: Why do psychiatrists have such high suicide rates?
A: Psychiatrists face unique stressors, including direct exposure to patient suicides, ethical dilemmas in treatment limits, and the emotional toll of managing severe mental illness. Additionally, they are more likely to be diagnosed with depression themselves but may struggle to seek help due to professional stigma. Studies suggest that up to 40% of psychiatrists experience burnout, with suicide rates 40% higher than other physicians.
Q: Are female physicians at higher risk than male physicians?
A: Yes. While male physicians historically had higher suicide rates, recent data shows that female physicians—particularly in specialties like OB-GYN and primary care—now report higher rates of depression and suicidal ideation. This shift is attributed to increased willingness to seek help, higher rates of burnout in female-dominated fields, and the compounded stress of work-life balance issues. However, male physicians still die by suicide at higher rates due to later-stage intervention (e.g., substance use masking depression).
Q: How does medical training contribute to suicide risk?
A: Medical training is designed to prioritize endurance over well-being, with residents often working 80+ hour weeks while managing high-stakes patient care. This environment normalizes sleep deprivation, emotional detachment, and perfectionism—all of which are linked to long-term mental health decline. Specialties with longer training periods (e.g., psychiatry, surgery) see higher burnout rates, as the culture of "toughing it out" becomes ingrained early in a physician’s career.
Q: What can be done to reduce suicide rates in medicine?
A: Effective strategies include:
- Mandatory mental health training in medical schools and residencies, not as optional electives.
- Peer support networks (e.g., The Doctors Company’s programs) with confidential, stigma-free resources.
- Policy changes to remove barriers to mental health care, such as insurance parity for physicians and protected leave for therapy.
- Cultural shifts in medical workplaces, where asking for help is normalized—not seen as a sign of weakness.
- Early intervention programs for specialties with high risk, such as psychiatry and EM, where moral injury is rampant.
Q: Are there specialties with lower suicide rates?
A: Yes, but the differences are often more about workplace culture than inherent risk. Specialties like pediatrics, dermatology, and radiology tend to have lower suicide rates, partly because they involve less direct patient trauma and more structured, less emotionally taxing environments. However, even these fields are not immune—burnout and suicide risk still exist, though at reduced levels. The key factor appears to be lower exposure to moral injury and higher job satisfaction, which suggests that workplace conditions play a larger role than the specialty itself.
