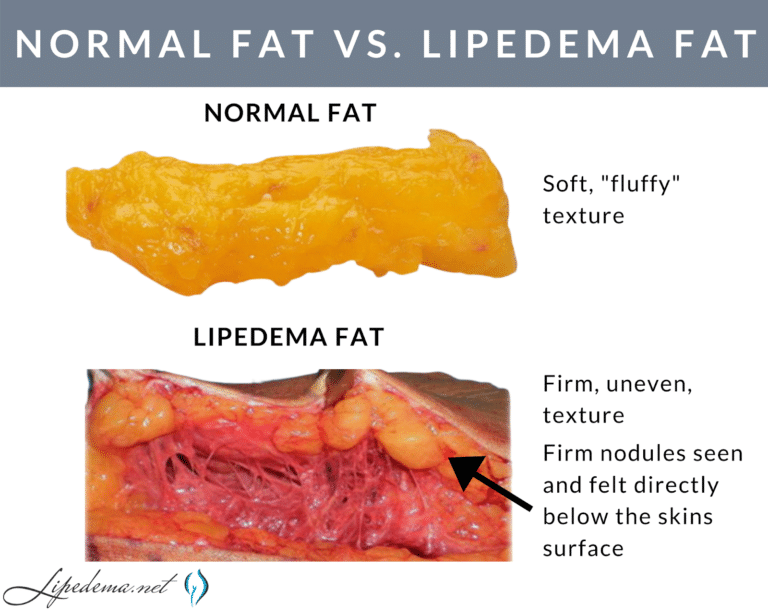
The Complete Overview of Lipedema Fat Vs Normal Fat
Lipedema fat and normal fat share a common origin—adipose tissue—but diverge in critical ways. Normal fat serves as energy storage, insulation, and hormonal regulation, adapting to caloric intake and physical activity. Lipedema fat, however, operates on a different script: it expands independently of dietary changes, resists liposuction in conventional forms, and often coexists with other lymphatic disorders. The misclassification stems from early medical assumptions that fat was fat, regardless of origin. The turning point came in the 1940s when German physician Dr. Allen described lipedema as a distinct condition, though it took decades for Western medicine to recognize it. Today, research confirms that lipedema fat cells (adipocytes) produce pro-inflammatory cytokines at higher rates, contributing to fibrosis and pain. This isn’t just excess weight; it’s a chronic inflammatory state disguised as obesity.Historical Background and Evolution
Lipedema’s journey from obscurity to medical acknowledgment reveals how deeply entrenched biases shape diagnosis. In the 19th century, physicians like Dr. Hermann von Helmholtz noted that some women developed "fat legs" resistant to weight loss, but the condition was sidelined as a female vanity issue. It wasn’t until the 1970s that American researchers began documenting cases systematically, linking lipedema to lymphatic dysfunction and hormonal imbalances. The breakthrough came with tunable (water-jet) liposuction, a technique developed in the 1990s specifically for lipedema. Unlike traditional liposuction, which targets subcutaneous fat, tunable liposuction preserves deeper structures while removing the fibrous, water-logged lipedema fat. This innovation forced a reckoning: lipedema wasn’t a lifestyle problem but a structural one, requiring surgical precision. The evolution from dismissal to specialized treatment mirrors broader shifts in how medicine views chronic conditions in women.Core Mechanisms: How It Works
The difference between lipedema fat and normal fat lies in cellular behavior. Normal adipocytes store triglycerides and release them when energy is needed, regulated by insulin and leptin. Lipedema adipocytes, however, proliferate uncontrollably, forming dense, fibrous deposits that disrupt lymphatic flow. This isn’t just fat; it’s a tumor-like growth of adipose tissue, often with abnormal blood vessel formation. The trigger remains unclear, but genetic predisposition, hormonal fluctuations, and lymphatic insufficiency play roles. Unlike normal fat, which responds to caloric deficits, lipedema fat persists because its growth isn’t tied to energy storage but to dysregulated signaling pathways. This explains why diet and exercise alone rarely resolve lipedema—its biology is fundamentally different.Key Benefits and Crucial Impact
Recognizing the distinction between lipedema fat and normal fat transforms patient outcomes. For years, women with lipedema endured mockery for their inability to "just lose weight," while doctors prescribed fad diets that worsened their pain. The shift toward specialized care—combining tunable liposuction, lymphatic drainage, and compression therapy—has restored mobility and self-esteem to thousands. The economic impact is staggering: reduced healthcare costs from avoided surgeries, improved productivity, and diminished mental health burdens. The psychological toll of misdiagnosis is incalculable. Lipedema patients often develop body dysmorphia, depression, and social withdrawal, believing they lack willpower. Correct diagnosis and targeted treatment disrupt this cycle, proving that fat isn’t fat—it’s a medical condition with specific solutions."Lipedema isn’t a weight problem; it’s a structural one. Until we stop treating it like obesity, we’ll keep failing patients." — Dr. Michael Zerr, Lipedema Specialist
Major Advantages
- Precision treatment: Tunable liposuction removes only lipedema fat, preserving normal adipose tissue and reducing recovery time.
- Pain relief: Addressing lymphatic congestion alleviates the deep, aching discomfort that defines lipedema.
- Improved mobility: Fibrous deposits compressing nerves are excised, restoring range of motion.
- Mental health benefits: Correct diagnosis eliminates shame and replaces it with actionable solutions.
- Reduced surgical risks: Unlike general obesity surgery, lipedema-specific procedures target only affected areas.
- Long-term stability: Post-treatment maintenance focuses on lymphatic health, not caloric restriction.
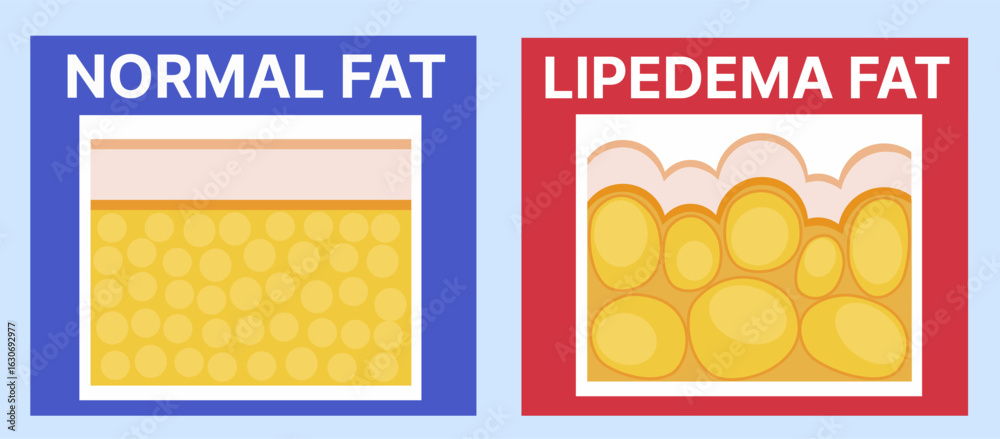
Comparative Analysis
| Lipedema Fat | Normal Fat |
|---|---|
| Accumulates in legs, arms, buttocks; spares torso | Distributes uniformly across body |
| Resistant to diet/exercise; requires surgical intervention | Responds to caloric deficits and physical activity |
| Associated with fibrosis, pain, and lymphatic dysfunction | Primarily energy storage with minimal systemic impact |
| Diagnosed via clinical exam, not BMI or imaging | Assessed through BMI, waist-to-hip ratio, and body fat percentage |
| Treated with tunable liposuction, lymphatic therapy | Managed via nutrition, exercise, and lifestyle changes |
Future Trends and Innovations
The next frontier in lipedema research lies in genetic and lymphatic therapies. Studies suggest that lipedema may share pathways with lymphedema and even certain cancers, where adipose tissue undergoes uncontrolled growth. Advances in stem cell therapy and anti-fibrotic drugs could offer non-surgical options, while AI-driven diagnostics may improve early detection. The goal isn’t just cosmetic correction but reversing the underlying pathology. Patient advocacy is accelerating progress. Online communities and support groups have pushed for insurance coverage of tunable liposuction, reducing financial barriers. As awareness grows, so does the pressure on medical institutions to stop conflating lipedema with obesity—a distinction that could redefine chronic disease treatment.
Conclusion
The divide between lipedema fat and normal fat isn’t just academic; it’s clinical. Ignoring this difference has left millions in pain, misdiagnosed, and untreated. The science is clear: lipedema is a separate metabolic disorder, not a failure of willpower. Specialized treatments exist, but access remains uneven. The future depends on dismantling stigma, funding research, and treating lipedema as the medical condition it is. For patients, the message is simple: fat isn’t fat. What you’ve been told is "obesity" may be lipedema—and the solutions are waiting.Comprehensive FAQs
Q: Can lipedema fat be lost through diet alone?
No. Lipedema fat is metabolically distinct and doesn’t respond to caloric restriction like normal fat. Diet may improve overall health but won’t reduce lipedema deposits.
Q: Why do doctors often misdiagnose lipedema as obesity?
Lack of awareness and training lead to reliance on BMI, which doesn’t account for asymmetrical fat distribution. Many physicians remain unaware of lipedema’s unique symptoms and treatments.
Q: Is tunable liposuction covered by insurance?
Coverage varies by region and insurer. Some policies classify it as cosmetic, while others recognize it as medically necessary for chronic pain and mobility issues. Patient advocacy groups often provide guidance on appeals.
Q: Can lipedema progress into lymphedema?
Yes. Lipedema’s lymphatic dysfunction can worsen over time, leading to lymphedema—a secondary condition requiring additional treatment. Early intervention is critical to prevent this progression.
Q: Are there non-surgical treatments for lipedema?
Current options include compression therapy, manual lymphatic drainage, and low-level laser therapy, which may reduce symptoms but don’t eliminate fat deposits. Research into pharmaceuticals is ongoing.
Q: How is lipedema different from cellulite?
Cellulite involves localized fat dimpling due to connective tissue structure, while lipedema is a systemic disorder with pain, swelling, and disproportionate fat accumulation. Cellulite is cosmetic; lipedema is pathological.
Q: Can men have lipedema?
Extremely rare. Lipedema is overwhelmingly female, with cases in men often linked to hormonal disorders or genetic mutations. The condition’s hormonal triggers remain under study.
