
7 Things Worth Knowing About the Difference Between Medical Assistant and Nurse
The core differences between medical assistant and nurse reveal themselves in seven critical areas: education, certification, scope of practice, patient interaction, salary expectations, career advancement, and workplace settings. Each factor intersects with the others, creating a web of distinctions that define not just what these professionals do, but how they do it—and the consequences of those choices for patients and providers alike.1. Education and Training Requirements
Medical assistants typically complete 6-month to 2-year programs accredited by organizations like the Commission on Accreditation of Allied Health Education Programs (CAAHEP). These programs blend classroom instruction with hands-on labs, covering medical terminology, anatomy, and basic clinical skills. Some states require formal certification (more on that below), but the foundational education is shorter and less rigorous than nursing programs. Nurses, however, undergo far more extensive training. Registered nurses (RNs) must earn an associate degree (ADN) or bachelor’s degree (BSN)—programs that take 2 to 4 years—and pass the National Council Licensure Examination for Registered Nurses (NCLEX-RN). Advanced practice nurses (APNs), including nurse practitioners (NPs), hold master’s or doctoral degrees and complete additional clinical hours. The education gap between medical assistant and nurse isn’t just about time; it’s about depth. Nurses study pathophysiology, pharmacology, and leadership in greater detail, preparing them for autonomous decision-making.2. Certification and Licensing
Certification for medical assistants varies by state. The Certified Medical Assistant (CMA) credential, offered by the American Association of Medical Assistants (AAMA), requires graduation from an accredited program and passing an exam. Some employers accept the Registered Medical Assistant (RMA) from the American Medical Technologists (AMT), but neither is universally mandatory. A few states mandate certification for MAs, but many hire based on training alone. Nurses, however, face licensing requirements that are non-negotiable. All 50 states require RNs to pass the NCLEX-RN and maintain an active license through continuing education. APNs must also meet state-specific protocols for prescribing medications or diagnosing conditions. The licensing divide between medical assistant and nurse is stark: one role’s credentials are optional in many places, while the other’s are legally enforced nationwide. This distinction carries weight in malpractice cases, where a nurse’s actions are subject to stricter scrutiny.3. Scope of Practice: What They Can (and Can’t) Do
The functional differences between medical assistant and nurse are perhaps most visible in their scope of practice. Medical assistants cannot: - Administer most medications (except topical or oral medications in some states, with physician oversight). - Perform complex wound care or suturing. - Interpret diagnostic tests like X-rays or lab results. - Develop patient care plans. Nurses, by contrast, can: - Administer injections, IV medications, and some controlled substances (with prescriber orders). - Assess patient symptoms, modify care plans within protocols, and recognize emergencies. - Perform procedures like catheter insertions, EKGs, and basic suturing. - Educate patients on chronic disease management. A 2022 survey by the American Nurses Association found that 68% of nurses report making independent clinical decisions daily, a responsibility MAs are explicitly barred from. The legal boundaries between medical assistant and nurse are codified in state nurse practice acts, which outline disciplinary actions for overstepping—penalties that don’t apply to MAs.4. Patient Interaction and Responsibility
Medical assistants often serve as patient navigators, handling intake, vital signs, and basic triage. Their role is reactive: they assist providers by preparing exam rooms, drawing blood, or measuring blood pressure. While they may answer medical questions, their responses are limited to pre-approved protocols. Nurses, however, engage in proactive patient care. They conduct health assessments, counsel patients on lifestyle changes, and often serve as case managers for chronic conditions. A nurse might spend 20 minutes educating a diabetic patient on insulin administration; an MA would likely refer the patient to a nurse or physician for that discussion. The interaction dynamics between medical assistant and nurse reflect their training: MAs support the workflow, while nurses drive it.5. Salary and Earning Potential
Compensation reflects the difference between medical assistant and nurse in tangible ways. According to the U.S. Bureau of Labor Statistics (2023): - Medical assistants earn median wages around $38,000 annually, with the top 10% making approximately $50,000. - Registered nurses earn median wages near $86,000, with the top decile exceeding $128,000. - Nurse practitioners, with advanced degrees, report median salaries around $125,000, with some specialties (e.g., psychiatric or geriatric NP) earning significantly more. The pay disparity between medical assistant and nurse isn’t just about base salaries—it extends to overtime opportunities, shift differentials, and bonuses tied to patient outcomes. Nurses in critical care or operating rooms often earn 20–30% more than their MA counterparts in similar settings, due to the complexity of their roles.6. Career Advancement and Specialization
Medical assistants have fewer upward mobility paths. Some transition into specialized roles like medical coding, office management, or sales in healthcare tech, but these require additional certifications. Others pivot to nursing school after gaining clinical experience, though the leap is significant. Nurses enjoy clearer career ladders. RNs can advance to: - Charge nurse (supervisory role). - Clinical nurse specialist (expert in a niche like oncology). - Nurse educator (teaching future nurses). - Nurse administrator (managing healthcare facilities). Advanced practice nurses (NPs, CNMs, CRNAs) can open private practices, prescribe medications, and even specialize in surgery or anesthesia. The career trajectory difference between medical assistant and nurse is a major factor for those investing in education: nursing offers both vertical and horizontal growth, while MA roles often plateau without further study.7. Workplace Settings and Demand
Medical assistants are primarily found in outpatient clinics, physician offices, and urgent care centers. Their roles are designed for high-volume, low-acuity environments where efficiency matters more than complex interventions. Demand for MAs is steady but not projected to grow as rapidly as nursing roles, according to the BLS. Nurses work across all healthcare settings, from hospitals and long-term care facilities to schools, corporate wellness programs, and military bases. The versatility difference between medical assistant and nurse is critical: nurses are deployed in emergencies, surgeries, and public health crises, while MAs rarely operate outside structured clinic hours. The nursing shortage—exacerbated by retirements and burnout—has created high demand for RNs, with some hospitals offering sign-on bonuses exceeding $20,000.
How These Facts Connect
The difference between medical assistant and nurse isn’t isolated to one factor; it’s a cumulative effect of education, authority, pay, and opportunity. Short training and limited scope mean MAs fill a niche: they’re the backbone of primary care but can’t replace nurses in acute or complex settings. Nurses, with their broader training and legal protections, occupy a gatekeeper role—they assess, intervene, and educate in ways MAs cannot. This division isn’t arbitrary. It reflects centuries of healthcare evolution, where medical assistants emerged as cost-effective support staff while nursing developed as a regulated, autonomous profession. The overlap in duties—like taking blood pressure or administering vaccines—can create friction, but the core distinction between medical assistant and nurse remains clear: one assists; the other assesses and acts independently. For patients, this means trusting nurses with higher-stakes decisions. For employers, it means structuring teams where MAs handle routine tasks and nurses manage critical care.| Factor | Medical Assistant | Nurse (RN/APN) |
|---|---|---|
| Education | 6 months–2 years (diploma/certificate) | 2–4 years (ADN/BSN) + NCLEX; APNs require master’s/doctorate |
| Certification | Optional in many states (CMA/RMA) | Mandatory nationwide (NCLEX + state license) |
| Scope of Practice | Basic procedures, administrative tasks, patient prep | Diagnosis, treatment planning, medication administration, patient education |
| Salary Range (U.S.) | $30K–$50K (median ~$38K) | $70K–$130K+ (RN median ~$86K; NP median ~$125K) |
Conclusion
Choosing between a career as a medical assistant or a nurse isn’t just about personal preference—it’s about aligning your skills with the demands of the role. Medical assistants provide essential support in healthcare settings where speed and organization matter, but their limitations can be frustrating for those seeking deeper clinical involvement. Nurses, with their expanded responsibilities and higher earning potential, offer a path for those willing to invest more time and effort into their education. The difference between medical assistant and nurse ultimately boils down to autonomy and impact. Medical assistants are the gears that keep clinics running smoothly; nurses are the clinicians who shape patient outcomes. Both are vital, but their roles serve distinct purposes in the healthcare ecosystem. For prospective students, the decision hinges on how far you want to go—not just in terms of paychecks, but in terms of how much responsibility you’re ready to take on.Comprehensive FAQs
Q: Can a medical assistant become a nurse?
A: Yes, many MAs transition to nursing by leveraging their clinical experience. Some states offer bridge programs for MAs to earn ADN or BSN degrees in 1–2 years, bypassing foundational courses. Others enter RN programs directly after gaining experience. The CMA credential isn’t required for admission, but clinical hours may count toward nursing school prerequisites.
Q: Do medical assistants work under nurse supervision?
A: In most settings, yes. While MAs report to physicians or nurse practitioners, their day-to-day supervision often falls to RNs, especially in clinics where nurses oversee multiple MAs. However, the legal hierarchy between medical assistant and nurse is less formal than the physician–nurse relationship. MAs cannot delegate tasks to nurses but may assist them in procedures like wound care.
Q: Which role has better job security?
A: Nurses generally enjoy greater job security due to their broader skill set and critical role in patient care. The nursing shortage has created openings across specialties, while MA demand is tied to physician office growth—slower than hospital or home health sectors. That said, specialized MAs (e.g., in podiatry or ophthalmology) can find stable niches with high demand.
Q: Can a medical assistant administer medications?
A: It depends on state laws and employer policies. Some MAs in clinics can give oral or topical medications (e.g., antibiotics, creams) under physician orders, but injectable drugs typically require RN or LPN oversight. States like California restrict MAs from administering any medications unless under direct supervision. Always check local regulations before assuming authority.
Q: How do medical assistants and nurses collaborate in a clinic?
A: Their collaboration follows a defined workflow. Nurses often assess patients first, then delegate routine tasks (e.g., vitals, blood draws) to MAs while focusing on complex care. In team-based care models, MAs may assist nurses with procedures like EKGs or glucose monitoring, but nurses retain final authority on patient plans. Poor communication between the two can lead to medication errors or missed diagnoses, so clinics emphasize cross-training.
Q: Which role is more physically demanding?
A: Nurses typically face higher physical demands, especially in hospitals where they lift patients, stand for long shifts, and respond to emergencies. Medical assistants in clinics have less strenuous roles, though urgent care MAs may assist with procedures requiring dexterity. However, both roles involve repetitive motions (e.g., typing, drawing blood) that can lead to strain over time.
Q: Are there hybrid roles that blend MA and nurse duties?
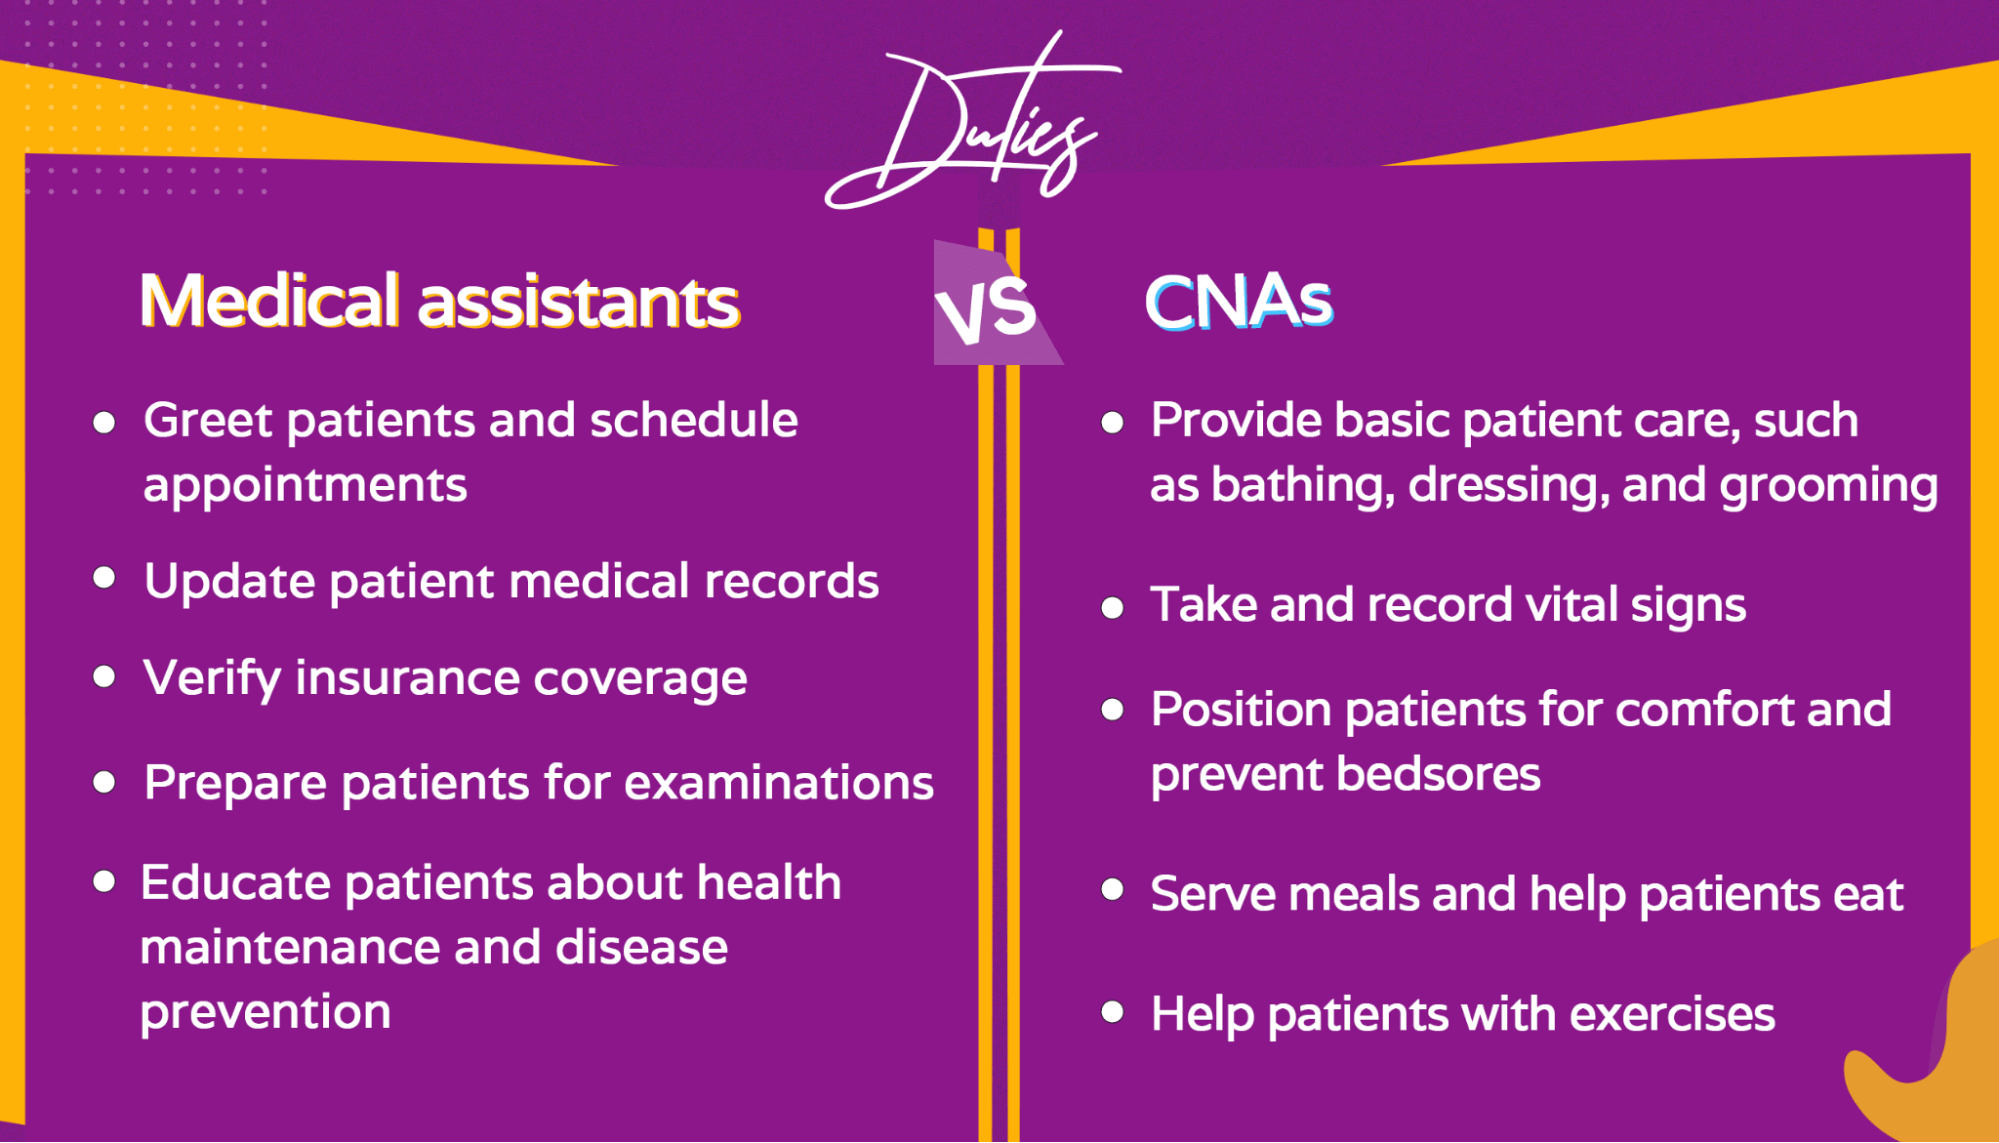
A: Yes, though they’re rare. Certified Nursing Assistants (CNAs) overlap with MAs in some settings, but CNAs focus on basic patient care (bathing, feeding) rather than clinical tasks. Physician assistants (PAs)—who require master’s degrees—perform nurse-like duties but with physician-level authority. Some hospitals create expanded MA roles (e.g., "clinical assistant") to handle more procedures, but these require additional training and often higher pay.
Q: What’s the biggest misconception about the difference between medical assistant and nurse?
A: The most persistent myth is that medical assistants are "junior nurses." In reality, their training and legal scopes are fundamentally different. Another misconception is that nurses only perform clinical tasks—many RNs spend time on administration, education, or research, while MAs rarely engage in patient education beyond basic instructions. Clarifying these role distinctions helps patients and employers set realistic expectations.
