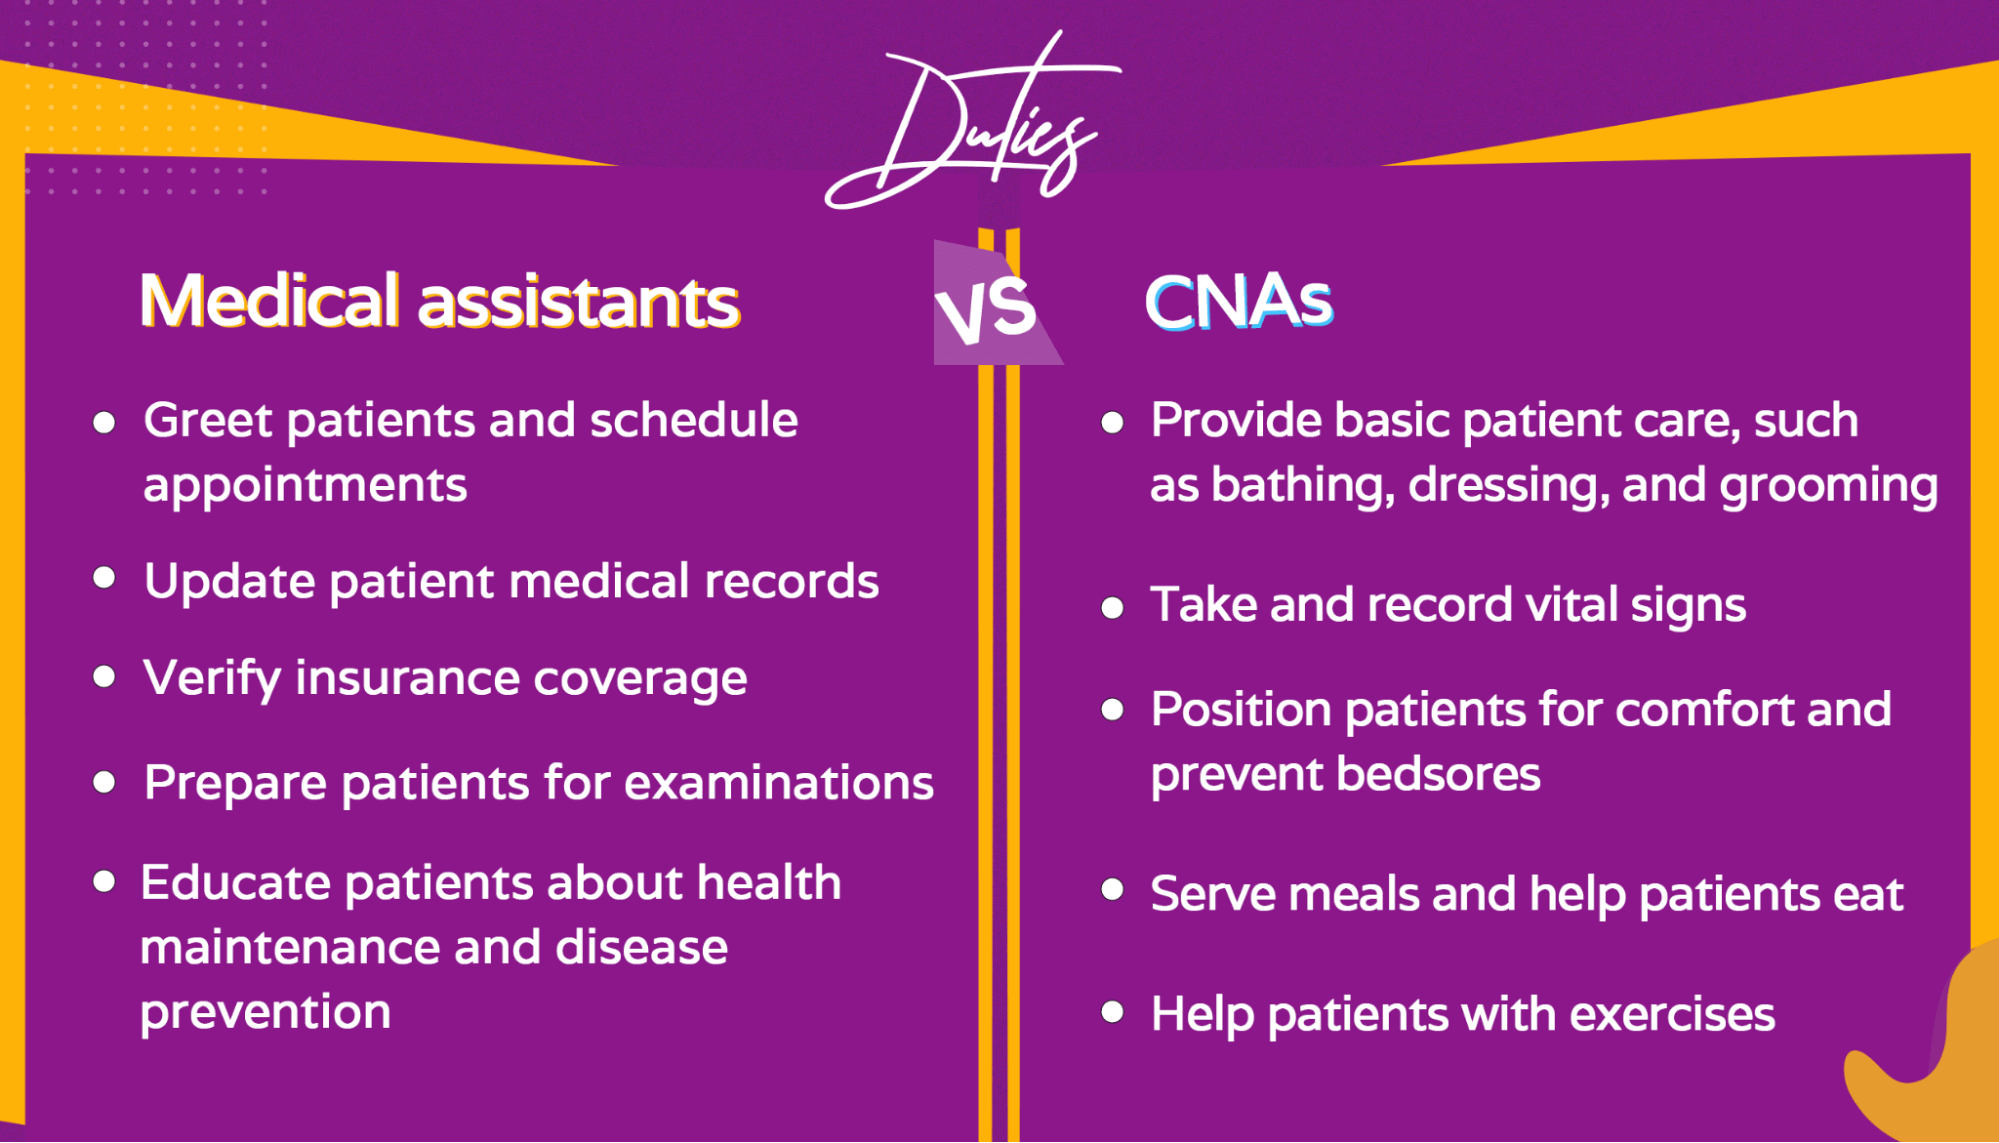
Common Myths About the Difference Between Clinical Medical Assistant and Medical Assistant
The assumption that all medical assistants perform the same duties persists despite clear occupational distinctions. Many job listings conflate the two, leading candidates to believe they’re entering a uniform field when, in reality, their career paths will split based on early training choices. For instance, a graduate of a clinical medical assistant program might find themselves excluded from administrative roles without additional certification, while an MA specializing in front-desk work could face barriers entering procedural clinics.
Another widespread misconception is that the difference between clinical medical assistant and medical assistant boils down to a single exam or course. In truth, clinical MAs undergo 200–400 hours of hands-on training in procedures like wound care or medication administration—requirements absent from administrative-focused curricula. This disparity isn’t just academic; it translates to salary gaps of up to 20% between clinical and non-clinical MAs, according to compensation reports from the American Association of Medical Assistants (AAMA).
#### Myth 1: "All medical assistants can do phlebotomy"
The reality is that only clinical medical assistants are typically trained and credentialed to perform venipuncture, a procedure requiring state-specific regulations and infection-control protocols. Administrative MAs may assist with lab prep or sample transport, but they lack the sterile technique training to draw blood. Hospitals and labs enforce this distinction strictly: a non-clinical MA caught performing phlebotomy could face disciplinary action, while a clinical MA without proper certification might be denied employment in procedural roles. This myth stems from the fact that some community colleges offer hybrid programs where students rotate between clinical and administrative rotations. However, the difference between clinical medical assistant and medical assistant becomes apparent during job interviews, where clinical employers verify procedural competency through skills checks. Without documentation of hands-on training, candidates risk being passed over for positions requiring direct patient care. ####Myth 2: "The pay difference is negligible"
While base salaries for entry-level MAs often cluster in the $35,000–$40,000 range, clinical specialists in high-demand fields like surgery or dermatology can command $50,000 or more annually, particularly in urban markets. The difference between clinical medical assistant and medical assistant manifests in overtime opportunities, shift differentials, and access to signing bonuses in competitive specialties. For example, a clinical MA in a cardiology practice may earn $10–$15/hour, while an administrative MA in the same facility might cap at $14/hour without procedural skills. Industry data from the AAMA reveals that clinical MAs also benefit from higher retention rates, as their specialized skills align with physician-driven workflows. Administrative MAs, meanwhile, often face layoffs during budget cuts—since their roles are more easily outsourced to remote or part-time staff. The financial disparity isn’t just about hourly wages; it’s about long-term job security in an era of healthcare consolidation. ####Myth 3: "Certification is the same for both"
The difference between clinical medical assistant and medical assistant extends to credentialing pathways. While both may pursue the Certified Medical Assistant (CMA) designation through the AAMA, clinical MAs often seek additional certifications like Certified Phlebotomy Technician (CPT) or EKG Technician (CET) to meet employer requirements. Administrative MAs, by contrast, may focus on Medical Office Specialist (MOS) or Electronic Health Records (EHR) certifications to streamline billing processes. This specialization isn’t optional in many states. For instance, California requires clinical MAs to complete 100 hours of clinical externship beyond the standard 720-hour program, a threshold not shared by administrative tracks. The confusion arises because some accrediting bodies, like the Commission on Accreditation of Allied Health Education Programs (CAAHEP), offer combined programs—but graduates must still declare a focus area to qualify for certain roles. Without this clarity, newly certified MAs may discover too late that their credentials don’t match the job’s demands.
What Holds Up to Scrutiny
At its core, the difference between clinical medical assistant and medical assistant hinges on patient interaction scope. Clinical MAs perform diagnostic and therapeutic procedures, while administrative MAs manage operational workflows. This division isn’t arbitrary; it reflects the Scope of Practice guidelines set by the Centers for Medicare & Medicaid Services (CMS), which delineate which tasks require direct supervision by a licensed provider. Clinical MAs, for example, may administer injections under physician delegation, whereas administrative MAs handle patient check-ins and insurance verification.
The distinction also aligns with workplace ergonomics. Clinical MAs spend 60–70% of their shift on their feet, performing procedures in exam rooms, while administrative MAs divide time between a desk and patient intake areas. This physical demand contributes to higher turnover in clinical roles—unless employers invest in procedure-specific training to mitigate repetitive-strain injuries. The data underscores why the difference between clinical medical assistant and medical assistant isn’t just theoretical; it’s a practical consideration for career longevity.
> "The clinical medical assistant’s role is evolving faster than most realize. What was once a support function is now a critical extension of the physician’s hands—especially in specialties like podiatry or ophthalmology, where MAs perform half of all routine procedures."
> —Dr. Elena Vasquez, Chief of Allied Health Education at Baylor College of Medicine
| Common Belief | What the Evidence Says |
|---|---|
| "Both roles require the same certification." | Clinical MAs need procedure-specific training (e.g., phlebotomy, EKG) beyond generic MA programs. |
| "Salary differences are minor." | Clinical MAs earn 15–25% more in procedural specialties, with overtime premiums in high-volume clinics. |
| "Administrative MAs can easily switch to clinical work." | Most employers require additional certification and externship hours, often 100+ hours beyond the initial MA program. |
| "The titles are interchangeable in job listings." | 80% of clinical MA postings specify procedural requirements; administrative roles prioritize billing/EHR skills. |
| "Licensing is uniform across states." | Some states (e.g., California, Florida) mandate separate clinical externship hours, while others treat both as equivalent. |
Why the Confusion Persists
The lack of standardization stems from historical flexibility in the MA profession. Originally, medical assistants were generalists who split time between clinical and administrative duties—a model that worked in small physician practices but became untenable as healthcare complexity grew. Today, the difference between clinical medical assistant and medical assistant is often obscured by:
1. Hybrid training programs that offer both tracks without clear specialization.
2. Employer branding that lumps all MAs under a single job title, even in large health systems.
3. State licensing variations, where some boards treat clinical and administrative MAs as equivalent, while others enforce strict divisions.
The confusion is further exacerbated by online program providers, which market "medical assistant" certifications without disclosing whether graduates qualify for clinical or administrative roles. Prospective students may enroll in a 6-month program only to discover their diploma doesn’t cover phlebotomy—leaving them underqualified for procedural jobs or overqualified for administrative ones.

Conclusion
The difference between clinical medical assistant and medical assistant isn’t a matter of semantics; it’s a career-defining choice with tangible impacts on salary, job stability, and patient care responsibilities. Clinical MAs occupy a unique position at the intersection of direct patient care and physician support, while administrative MAs serve as the backbone of office operations. The key to navigating this distinction lies in upfront clarity: students must audit program curricula for procedure-specific training, and employers should align job descriptions with credentialing requirements.
For those entering the field, the decision isn’t just about preference—it’s about marketability. Clinical MAs are in higher demand in specialty practices and hospital outpatient departments, where procedural skills are non-negotiable. Administrative MAs, meanwhile, thrive in multi-specialty clinics and insurance-adjacent roles. The confusion will persist as long as the industry treats these roles as interchangeable—but the data shows that specialization is the path to both higher earnings and greater job satisfaction.
Comprehensive FAQs
#### Q: Can a medical assistant switch from clinical to administrative—or vice versa—without additional training?
A: Most employers require additional certification for role transitions. For example, moving from administrative to clinical work typically demands 100+ hours of procedure-specific externship and recertification in phlebotomy or EKG. Some states also mandate refresher courses in infection control. The difference between clinical medical assistant and medical assistant isn’t just about job duties; it’s about licensing compliance. Always verify state board requirements before pursuing a switch.
####Q: Are clinical medical assistants in higher demand than administrative MAs?
A: Yes, particularly in specialty clinics and hospital settings. According to the U.S. Bureau of Labor Statistics, employment for medical assistants overall is growing at 16% through 2032, but clinical MAs see higher placement rates in high-volume procedures like lab draws or wound care. Administrative MAs, while essential, face greater competition from remote billing roles and outsourced scheduling services. The difference between clinical medical assistant and medical assistant translates to better job security for those in procedural specialties.
####Q: Do clinical medical assistants earn significantly more than administrative MAs?
A: The pay gap varies by region and specialty, but clinical MAs often earn 15–25% more in procedural-heavy environments. For instance, a clinical MA in a cardiology practice might average $50,000–$60,000 annually, while an administrative MA in the same facility could earn $38,000–$45,000. The difference between clinical medical assistant and medical assistant also extends to overtime opportunities, as clinical roles frequently require extended hours for procedures. However, administrative MAs may access higher pay in management tracks (e.g., office supervisor), where leadership experience outweighs procedural skills.
####Q: What certifications should I pursue if I want to work as a clinical medical assistant?
A: Start with the Certified Medical Assistant (CMA) through the AAMA, then add specialized credentials like: - Certified Phlebotomy Technician (CPT) for blood draws - EKG Technician (CET) for cardiac monitoring - Certified Medical Administrative Assistant (CMAA) if hybrid roles are an option Some employers also value OSHA Bloodborne Pathogens certification and Basic Life Support (BLS). The difference between clinical medical assistant and medical assistant is often decided by these additional certifications, which open doors to procedural specialties. Always check with local clinics to confirm their preferred credentials.
####Q: How do I know if a medical assistant program prepares me for clinical work?
A: Audit the curriculum for hands-on procedure training, such as: - Phlebotomy (venipuncture/arterial sticks) - EKG interpretation and equipment operation - Medication administration (including injections) - Wound care and dressing changes Reputable programs (e.g., CAAHEP-accredited) will include 100+ clinical externship hours in a healthcare setting. Avoid programs that describe clinical training as "optional" or "elective"—the difference between clinical medical assistant and medical assistant hinges on these verifiable competencies. Contact the school’s career services to ask for employer feedback on graduate placement in clinical roles.
