
Common Myths About What Is the Primary Role of Communication in Enhancing Health
The assumption that health communication is purely transactional—merely the exchange of medical facts—persists even as research dismantles it. Many still believe that what is the primary role of communication in enhancing health reduces to pamphlets and public service announcements, when in reality, the most critical exchanges happen in unscripted moments: a doctor pausing to ask how a patient’s stress levels affect their blood pressure, a neighbor checking in after a diagnosis, or a social media post that normalizes seeking therapy. The transactional view ignores that health behaviors are emotional decisions. A study in The Lancet found that patients who perceived their doctors as empathetic were twice as likely to follow lifestyle recommendations—because the message wasn’t just heard, it was felt. Another myth treats communication as a one-way street. The idea that health professionals "deliver" information to passive recipients ignores that meaning is co-created. A 2021 review in Social Science & Medicine highlighted how patient narratives—when actively solicited—can uncover barriers to care that clinical data misses. For example, in rural Appalachia, residents struggling with opioid dependence often described stigma as a greater obstacle than addiction itself. Only by listening did providers realize that what is the primary role of communication in enhancing health there wasn’t just about medication; it was about restoring dignity. Similarly, in digital health, algorithms that push generic advice without adapting to user psychology fail because they treat communication as a broadcast, not a dialogue. A third misconception frames communication as a luxury, reserved for high-resource settings. The opposite is true: where resources are scarce, communication becomes the most potent tool. In post-conflict regions, for instance, trauma-informed storytelling has been shown to reduce PTSD symptoms more effectively than traditional therapy—because it validates experiences that were previously silenced. Even in wealthy nations, underserved communities often receive poor-quality communication from providers who assume literacy or cultural familiarity. The result? Misdiagnoses, non-adherence, and preventable crises. What’s often called a "health disparity" is, at its root, a communication gap.Myth 1: "Health communication is just about sharing facts"
The fact-focused view stems from a biomedical model where knowledge equals action. But research in behavioral economics shows that facts alone don’t change behavior—context does. A classic example: smokers who hear "smoking kills" are less likely to quit than those told "smoking will make you smell bad to your kids." The first message is factual; the second is emotionally anchored. Studies on vaccine hesitancy reveal a similar pattern. Anti-vaccine narratives often exploit cognitive dissonance—people reject science when it conflicts with their identity. What is the primary role of communication in enhancing health here isn’t to overwhelm with data but to reframe the conversation so that healthy choices align with values, not just statistics. Even in clinical settings, what’s said is less important than how it’s said. A 2020 study in Patient Education and Counseling found that doctors who used narrative framing—telling stories about other patients’ recoveries—helped patients with chronic illnesses adhere to regimens better than those who received dry instructions. The difference? Stories create empathic connection, making abstract advice feel personal. This isn’t about manipulating patients; it’s about meeting them where they are. The same principle applies to public health campaigns. A message about handwashing that focuses on protecting loved ones (emotional) is more effective than one about germ transmission (factual). Communication isn’t neutral; it’s a tool for shaping perception—and perception shapes health.Myth 2: "Digital communication replaces human interaction"
Telemedicine and AI chatbots have expanded access to care, but they’ve also reinforced the myth that what is the primary role of communication in enhancing health can be automated. The reality? Digital tools excel at efficiency; humans excel at nuance. A 2023 meta-analysis in JAMA Network Open found that while video consultations improved access for rural patients, those who used them reported higher rates of anxiety about their conditions—likely because nonverbal cues (tone, facial expressions) were lost. Meanwhile, AI-driven health apps often misdiagnose emotional distress as physical symptoms, leading to inappropriate self-treatment. What’s missing isn’t technology; it’s the human element of communication. The most successful digital health interventions integrate human touch. For example, text-message reminders for medication adherence work best when paired with personalized check-ins from nurses. Similarly, mental health apps like Woebot use conversational AI, but their highest engagement comes when users can opt into human therapist support. Even in low-resource settings, community health workers—not algorithms—are the backbone of effective communication. Their role isn’t to replace doctors but to bridge gaps where formal care is unavailable. What is the primary role of communication in enhancing health in these cases? It’s about restoring agency—helping people feel seen, not just served.Myth 3: "Clear communication is enough to change behavior"
Clarity is necessary but insufficient. What is the primary role of communication in enhancing health extends beyond intelligibility to cultural relevance, power dynamics, and emotional safety. A well-designed pamphlet in a clinic waiting room might explain diabetes management, but if the patient’s family dismisses the advice as "doctor’s orders," the message fails. This is why participatory communication—where communities co-design health messages—yields better results. In Kenya, for instance, HIV prevention campaigns that used local idioms and storytelling saw 40% higher condom use than those relying on Western-style public service announcements. Power imbalances also distort communication. A patient who fears judgment won’t disclose symptoms; a marginalized group won’t trust health authorities if past interactions were exploitative. What’s often called "non-compliance" is really non-consent—a breakdown in the relational contract between provider and patient. Even in well-intentioned settings, jargon and condescension can undermine trust. A study in Health Communication found that patients from non-dominant cultural backgrounds were more likely to distrust medical advice when delivered in a tone that implied their prior knowledge was inadequate. What is the primary role of communication in enhancing health here is to level the playing field—not just in information, but in respect.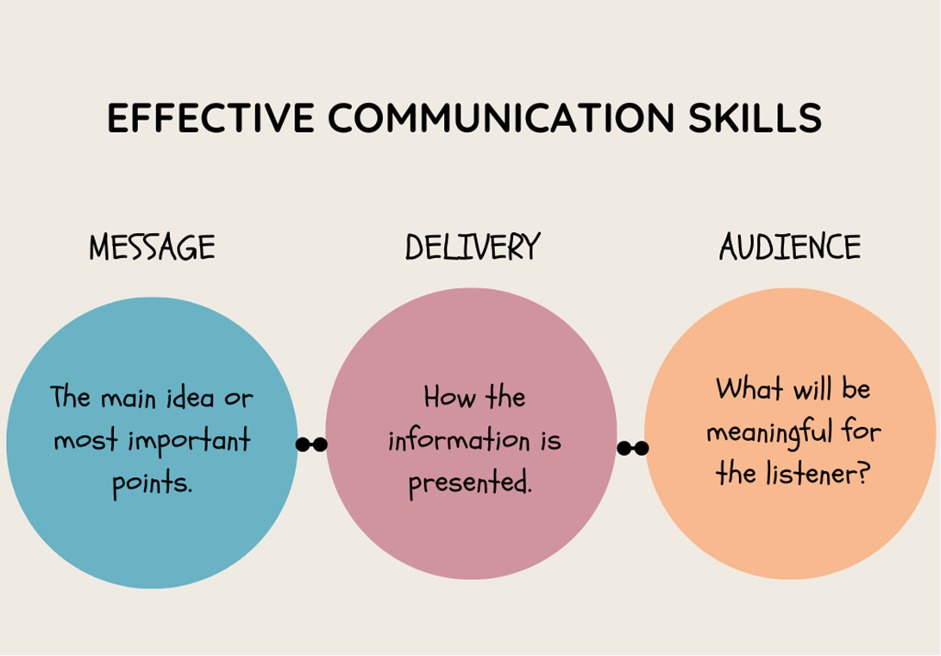
What Holds Up to Scrutiny
At its core, what is the primary role of communication in enhancing health is to reduce uncertainty. Uncertainty breeds stress, and chronic stress is a well-documented risk factor for heart disease, depression, and weakened immunity. When people understand their bodies, their risks, and their options, they make choices that align with their well-being. But this isn’t just about clarity—it’s about psychological safety. A patient who feels safe asking questions is more likely to follow through on treatment. A community where health rumors are addressed collectively sees higher vaccination rates. The evidence points to three non-negotiable pillars: 1. Trust as the foundation. Studies show that trust in healthcare providers predicts better outcomes than socioeconomic status. When patients believe their concerns will be heard, they engage more actively. 2. Two-way exchange over monologue. Health literacy programs that actively involve participants in shaping messages have higher retention rates. 3. Emotional resonance over neutrality. Messages that connect to identity, fear, or hope are more likely to prompt action. These aren’t abstract theories. They’re measurable effects seen across disciplines—from pediatric care to global pandemics."Health communication isn’t about persuasion; it’s about co-creation. The most effective messages aren’t those that tell people what to do, but those that help them understand why it matters to them." —Dr. Richard Frankel, University of Rochester Medical Center
| Common Belief | What the Evidence Says |
|---|---|
| Patients will follow advice if they understand it. | Understanding is necessary but not sufficient; emotional alignment (e.g., linking advice to values) drives adherence. |
| Digital tools can replace human interaction. | Automation improves access but human connection is critical for complex or sensitive issues. |
| Cultural differences don’t affect health communication. | Messages must be culturally adapted—idioms, metaphors, and power dynamics all influence reception. |
| Clear instructions eliminate confusion. | Clarity reduces ambiguity, but contextual relevance (e.g., linking advice to daily life) ensures retention. |
| Health communication is a public health function. | It’s a shared responsibility—communities, families, and individuals all shape health outcomes through dialogue. |
Why the Confusion Persists
The disconnect between theory and practice stems from institutional inertia. Medical training often prioritizes clinical skills over interpersonal communication, leaving providers ill-equipped to handle the emotional labor of care. Meanwhile, public health campaigns default to one-size-fits-all messaging, ignoring that what is the primary role of communication in enhancing health varies by audience. Even in research, studies frequently treat communication as a control variable—something to be standardized, not studied—rather than a dynamic force. Cultural biases also play a role. In many societies, silence is mistaken for compliance. A patient who nods but doesn’t ask questions may be assumed to understand, when in reality, they’re deferring to authority. Similarly, stigma around mental health leads to undercommunication—patients avoid discussing anxiety or depression because they fear judgment, even when those issues directly impact physical health. The result? Misdiagnoses, untreated conditions, and preventable suffering. The confusion isn’t just about what to say; it’s about when to listen.
Conclusion
What is the primary role of communication in enhancing health isn’t about delivering information—it’s about creating conditions where people can act on it. That means designing messages that resonate, building trust through empathy, and ensuring that every interaction—from a doctor’s consultation to a social media post—feels like a dialogue, not a lecture. The data is clear: where communication thrives, health outcomes improve. The challenge is scaling this insight beyond pilot programs into systemic change. The future of health communication lies in three shifts: 1. From monologue to conversation. Patients and communities must be active participants, not passive recipients. 2. From neutrality to relevance. Messages must connect to identity, culture, and lived experience. 3. From efficiency to empathy. Technology should augment, not replace, human connection. The evidence isn’t just compelling—it’s actionable. The question now is whether institutions will adapt.Comprehensive FAQs
Q: How does communication affect mental health specifically?
Mental health relies heavily on social validation and emotional processing. Studies show that people who feel heard and understood by others experience lower rates of depression and anxiety. Conversely, miscommunication or dismissal of emotional needs can exacerbate distress. For example, a 2021 study in Psychological Science found that couples who used active listening techniques reported 30% higher relationship satisfaction and lower cortisol levels—a key stress marker. Even in therapy, what is the primary role of communication in enhancing health is to create a space where clients feel safe expressing vulnerability, which directly impacts recovery.
Q: Can poor communication in healthcare lead to medical errors?
Absolutely. The Joint Commission, a U.S. patient safety organization, estimates that up to 80% of serious medical errors involve communication breakdowns. These can occur between doctors and patients (e.g., misdiagnosis due to unclear symptoms), between healthcare teams (e.g., missed test results), or between providers and support staff (e.g., medication errors from illegible handwriting). A 2020 study in BMJ Quality & Safety found that poor hand-off communication during shift changes in hospitals led to adverse events in 15% of cases. The solution isn’t just better training—it’s structured communication protocols, such as the SBAR method (Situation-Background-Assessment-Recommendation), which has been shown to reduce errors by 30% in some settings.
Q: How do cultural differences impact health communication?
Cultural norms shape how information is received, interpreted, and acted upon. For instance, in collectivist cultures (e.g., many Asian or Latin American societies), family input is often critical in health decisions—yet providers may overlook this by focusing solely on the patient. Conversely, in individualistic cultures, patients may prioritize autonomy, leading to friction if providers assume family involvement. What is the primary role of communication in enhancing health here is cultural humility—recognizing that what feels clear to one group may be confusing to another. Research in Health Communication shows that tailored messaging (e.g., using local idioms, involving community leaders) can improve adherence by up to 50% in diverse populations.
Q: Are there examples of successful health communication campaigns?
Yes, but they share key traits: participatory design, emotional resonance, and trust-building. One standout is Brazil’s "Bolsa Família" program, which combined cash transfers with community health worker (CHW) visits. The CHWs didn’t just deliver medical advice—they listened to families’ concerns, adapted messages, and built trust. As a result, childhood malnutrition rates dropped by 40% in participating regions. Another example is Australia’s "Quits" campaign, which used humor and storytelling to reduce smoking rates among youth. Instead of fear-based messaging, it framed quitting as a personal empowerment story, leading to a 12% decline in teen smoking within five years. Both cases prove that what is the primary role of communication in enhancing health isn’t about persuasion—it’s about co-creation and connection.
Q: How can individuals improve health communication in their own lives?
Start with active listening. Research shows that people feel more valued when they’re heard without interruption. For example, a spouse who says, "I hear that you’re stressed—tell me more" instead of "You’re overreacting" fosters healthier emotional processing. In healthcare settings, ask for clarification if instructions are unclear—studies show that patients who repeat back what they’ve been told have higher adherence rates. For public health, share credible sources (e.g., WHO or CDC) and avoid amplifying misinformation, even if it aligns with personal beliefs. Finally, normalize vulnerability—whether it’s discussing mental health or chronic illness. What is the primary role of communication in enhancing health at a personal level? It’s about reducing isolation and increasing agency.
